Tag Archives: peer support

National Cancer Caregiver Forum – October 2026 Update

by Matthew McKenzie FRSA BEM – Facilitator, National Cancer Caregiver Forum

Welcome to my October update from the National Cancer Caregiver Forum, which took place online on 28 October 2026.

For those unable to attend, this month’s session explored support for unpaid cancer carers, the role of hospice services, and why recognising a carer must lead to practical help. I welcomed colleagues from St Christopher’s Hospice, who explained their work with carers, families and communities.

I also shared an update on my engagement with Cancer Alliances and presented “Who Cares for the Cancer Carer?”, reflecting on the often unseen responsibilities of supporting someone living with cancer.

Building connections with Cancer Alliances

I opened the meeting by explaining why I am continuing to build relationships between the forum and Cancer Alliances.

Carers need opportunities to hear about support in their own areas, ask questions and influence services. A national forum can help make those connections, particularly when someone hears about good practice elsewhere and asks what is available locally.

On 27 October, I met with RM Partners, the West London Cancer Alliance, following questions about support for carers in West London.

We discussed identifying unpaid cancer carers, promoting the forum and creating opportunities for carers to contribute their experiences. RM Partners also described developing work around prehabilitation and rehabilitation, including physical activity, nutrition, information and psychological support.

An important question for me was how carers and families could contribute to this work. Their everyday knowledge can help services understand what happens between appointments and what makes support realistic to use.

I also updated the forum on my approach to North Central London Cancer Alliance, asking about support for cancer caregivers, opportunities for involvement and connections with our group. At the time of the October meeting, that conversation was still being developed.

The purpose of these links is to help carers find support and ensure their experiences influence how services develop.

St Christopher’s Hospice: support earlier in the journey

Our guests challenged a common assumption: that hospice care is only relevant during the final days of someone’s life.

They explained that St Christopher’s supports adults with life-limiting conditions, alongside their families and unpaid carers. Their presentation described support at home and within the hospice, working alongside other professionals involved in someone’s care.

A central message was that care involves more than managing physical symptoms. Emotional wellbeing, spiritual needs, relationships and personal wishes also matter.

For carers, understanding this earlier can make a difference. If people associate a hospice only with someone’s final days, they may not realise that there could be support worth exploring before that point.

The team described their work across Bromley, Croydon, Lambeth, Lewisham and Southwark, while explaining that access depends on the particular service and circumstances.

Community support and tackling inequalities

St Christopher’s community work includes addressing inequalities in access to palliative care and helping people understand what hospice support involves.

Our guests spoke about meeting communities, listening to concerns and responding to different understandings of illness, dying and bereavement.

This matters because information alone does not necessarily make a service accessible. People may have questions about whether a hospice understands their culture, beliefs or family circumstances. Others may simply not know whether the support is intended for them.

The team also described involving lived experience through consultation workshops, focus groups and an advisory panel. These provide opportunities to hear about barriers and use that learning to improve services.

This connected closely with the purpose of our forum: creating space for carers’ experiences to inform the support offered to them.

Support for unpaid carers

The presentation outlined several approaches to supporting carers, including peer groups, individual support and learning opportunities.

Carers Champion programme

The Carers Champion programme matches a carer with a volunteer who has lived experience of caring.

Our guests described a series of around six telephone conversations, offering space to talk, feel heard and reflect on the carer’s own wellbeing.

The examples shared illustrated the value of speaking with someone who understands caring from experience. A carer may find it difficult to express everything to family or friends, particularly when they are worried about upsetting others.

Having a separate space can help someone acknowledge feelings they have been carrying quietly.

Caring for Carers course

The team also described a free Caring for Carers course, delivered through three Zoom sessions.

Topics discussed included changing relationships, practical support and signposting, and loss or anticipatory grief.

Online delivery can make participation easier for some carers who struggle to leave home, although caring responsibilities can still make it difficult to find uninterrupted time.

At the meeting, the team said the next course was expected in February and offered to share further information for circulation.

Emotional support and anticipatory grief

We heard about support for anticipatory grief: the feelings someone may experience while preparing for the possible loss of a person they care about.

Carers may want to discuss those feelings, but they should also have the choice about when and whether to do so.

The presentation described bereavement buddy support and clinical services such as counselling, psychotherapy and art therapy, with access depending on the service and the person’s connection with St Christopher’s.

Can carers access support in their own right?

One question I raised was whether a cancer carer could receive support if the person they care for had not been referred to St Christopher’s.

Our guests explained that some community support, including carer groups and the Caring for Carers course, could be available more widely.

They also explained that the Carers Champion programme was not exclusively for carers of St Christopher’s patients, although capacity and waiting times needed to be considered. At the time of the meeting, they described a waiting list of approximately a month.

Clinical support for carers had different eligibility requirements and was linked to the person they supported being under St Christopher’s care.

This distinction is useful. Carers need clear information about which services they can approach directly, which require a referral and what they can expect next.

These details reflect the October presentation. Anyone interested should check current availability and eligibility with St Christopher’s.

Listening when carers say something has changed

I also asked how carers are involved in care planning and what happens when they tell staff that something has changed.

Carers often notice changes through their everyday involvement. They may recognise that someone is struggling, that a plan is becoming difficult to manage or that their own ability to continue caring has changed.

Our guests explained that detailed clinical arrangements sat with their clinical colleagues. They described assessments, advance care planning and opportunities for feedback through community work and consultation.

The discussion highlighted the importance of having a clear route for carers’ concerns. Inviting feedback is valuable, but carers also need to know who will respond and how their information will be used.

What happens when a carer feels unable to cope?

Another question concerned carers who feel exhausted or unable to manage at home, including outside normal working hours.

The team explained that St Christopher’s patients have an out-of-hours route for clinical concerns, including access to nursing advice.

For a carer’s own support needs, they described possible routes through their support programmes, social workers, GP and local services, depending on the situation.

We also discussed the distinction between the hospice’s own conversations and questionnaires with carers and a formal local authority carer’s assessment.

The presentation did not establish a general offer of respite. This remains an important question when carers need practical relief from their responsibilities as well as someone to talk to.

Matthew McKenzie: Who Cares for the Cancer Carer?

My presentation focused on the person supporting someone living with cancer.

People do not always describe themselves as carers. They may say they are a husband, wife, partner, daughter, son, sibling or friend. Their support may develop gradually, without a clear moment when they recognise how much they have taken on.

Yet around treatment and hospital appointments there can be another working day of responsibilities:

  • Arranging transport and accompanying someone to appointments.
  • Preparing meals and managing household tasks.
  • Making calls and following up information.
  • Remembering questions and keeping track of what happens next.
  • Balancing caring with employment, children or other family responsibilities.
  • Managing their own health alongside someone else’s needs.

These examples will not describe every carer. The point is to ask what someone is carrying that other people may not see.

Making room for the carer’s feelings

Caring can involve love and closeness alongside worry, frustration, uncertainty and exhaustion.

Those feelings can exist together. Carers should have space to describe their experience without being told how they ought to feel.

Some may feel guilty about asking for help. Others may worry that discussing their needs will add to the concerns of the person with cancer.

My message was that carers need room for their own experience too. They should not have to reach a crisis before someone asks how they are coping.

Within the forum, there is no expectation that someone must tell their full story. Listening, reflecting or contributing through the chat are all ways of taking part.

Recognition needs a practical next step

Recognising a carer is a starting point. What happens afterwards matters just as much.

A conversation about caring should help someone understand where to take their questions and what support they might explore.

Useful starting points can include:

  • “I support someone living with cancer. What support is available for me?”
  • “Who can I contact with my questions?”
  • “Could someone help me prepare for an appointment?”
  • “I am finding this difficult. What could help?”

For services, the corresponding questions are equally important: Who does this person rely on? What does their supporter need? What would make it easier for them to participate?

If someone says they are struggling, there needs to be clarity about who follows up.

Bridging the gap between knowing and accessing

A theme running through the meeting was the difference between knowing a service exists and feeling able to use it.

For one carer, a clear telephone contact may make the difference. Another may need written information to revisit later, language support or a session that fits around work and caring.

Someone else may first need reassurance that the service is relevant to their circumstances.

This is why asking “What would make this easier for you to access?” can be more useful than assuming that providing information has solved the problem.

Carers’ circumstances also change. Support that worked earlier in someone’s caring role may need to be reconsidered later.

Looking ahead

My thanks to the colleagues from St Christopher’s Hospice for sharing their work and answering questions about support for unpaid carers.

We discussed sharing presentation materials and course information, alongside the possibility of another visit to the forum in the new year.

I will also continue developing links with Cancer Alliances, helping connect carers with opportunities for support and involvement.

For anyone who could not attend, I hope this update offers useful questions to take into conversations with services. You are welcome to bring your experiences and questions to a future forum, or simply come along and listen.

What is one thing that would make your caring role more manageable?
Greenwich Mental Health Carers Forum – September 2026 Update

By Matthew McKenzie – Chair of the Greenwich Mental Health Carers Forum

Welcome to the September update of the Greenwich Mental Health Carers Forum, held on Tuesday 29 September 2026.

This month, we welcomed representatives from Greenwich Carers Centre, the Royal Borough of Greenwich, Healthwatch Greenwich and Greenwich Mental Health Hub, alongside unpaid carers.

Our discussion explored the future of carer support in Greenwich, difficulties accessing respite, support available through the Mental Health Hub, and how carers’ feedback can influence services.

Continue reading →

National Cancer Caregiver Forum – October 2026 Update

By Matthew McKenzie – Facilitator of Cancer Caregiver group

Welcome to the October update from my National Cancer Caregiver Forum, reflecting on our meeting held on 30 September.

I chair this forum to help bring greater attention to the experiences of people supporting someone living with cancer. Cancer care can involve a whirlwind of appointments, investigations, treatment decisions and changes at home. Behind all of this, family members, partners and friends often provide considerable practical and emotional support.

Yet their own needs can remain hidden.

Continue reading →

South West London Mental Health Carers Forum – September 2026 Update

By Matthew McKenzie, Co-Facilitator – South West London Mental Health Carers Forum

Our September forum brought carers together with Nisha from the South West London and St George’s Mental Health NHS Trust Recovery College.

We explored the courses available to carers, how to join them, and a question that matters well beyond the college: what happens when a carer still needs support after a time-limited service ends?

Continue reading →

South West London Mental Health Carers Forum – August 2026 Update

By Matthew McKenzie, Co-Facilitator – South West London Mental Health Carers Forum

The South West London Mental Health Carers Forum met again during August 2026, bringing together unpaid carers to share experiences, discuss how the forum is developing and look at ways we can strengthen the voice of carers across South West London.

The forum continues to be a peer-led space shaped by carers themselves. An important message from the August meeting was that this is a group for carers, run with carers and influenced by carers. Members spoke about wanting people who join the forum to feel recognised, valued and able to support one another, rather than the group becoming overly formal or service-led.

Continue reading →

Triangle of Care Community Meeting: July 2026 update

By Matthew McKenzie – Triangle of Care – Community group chair

Putting Carers at the Centre of Care

The latest Triangle of Care Community Group brought together carers, professionals and partner organisations from across England to share learning, celebrate progress and identify where further improvements are needed. The meeting highlighted the growing influence of the Triangle of Care across mental health and acute services, whilst reinforcing that there is still much work to do to ensure carers are consistently recognised, valued and supported.

One of the most powerful aspects of the meeting was hearing directly from carers about their experiences. Whilst many spoke positively about the progress that has been made over recent years, there was a shared view that carer involvement remains inconsistent across services.

Continue reading →

East Sussex Carers Voices – Celebrating Carers Week 2026

East Dean Village Hall – 11 June 2026

Written by Matthew McKenzie, Speaker, Carer, Campaigner and Poet

As part of Carers Week 2026, I had the privilege of travelling to East Dean in East Sussex to speak at the East Sussex Carers Voices – Celebrating Carers Week Event, organised by Care for the Carers. The event brought together unpaid carers, carers’ organisations, NHS representatives, local authority leaders, health professionals, community groups and carers from across East Sussex to discuss the realities of caring and identify ways to improve support for unpaid carers.

The event was hosted by Dr Neil Churchill, Chair of Care for the Carers, who guided the day’s discussions and emphasised the vital role carers play in society. Throughout the day, carers shared their personal stories, experiences and recommendations directly with decision-makers and service providers.

Continue reading →

Lewisham, Southwark & Lambeth carer forum update May 2026

Update by Matthew McKenzie – Chair of South London Mental Health Carers Forum

The South London Mental Health Carers Group met for the month of May for a wide-ranging and thoughtful discussion covering carers’ experiences, mental health support systems, involvement opportunities, and an important research presentation focused on support networks and long-term care.

The group covers areas of Lewisham, Southwark, Lambeth & Croydon, although Mental Health Carers from outside those areas are welcime to attend

The session brought together carers, advocates, involvement leads, and guest speaker Dr Anna De Simone from Queen Mary University of London. As always, the discussion highlighted both the challenges carers continue to face and the value of shared lived experience and peer support.

Opening Discussions: Challenges in Mental Health Care Systems

The meeting began with carers sharing experiences of navigating mental health services for loved ones with complex needs. There was extensive discussion around:

  • difficulties accessing appropriate placements,
  • safeguarding concerns,
  • discharge planning,
  • lack of continuity between NHS trusts and local authorities,
  • and ongoing challenges around funding responsibility between different services.

A recurring issue raised was the pressure on inpatient beds and the concern that discharge decisions can sometimes feel driven more by system pressures than by clinical readiness. Carers spoke openly about the emotional impact of repeatedly having to advocate for vulnerable loved ones while navigating fragmented systems.

There was also discussion around the importance of carers being recognised and included in communication and planning processes. Participants highlighted how carers are often the people most aware of deterioration, risks, or safeguarding concerns, and how vital it is that services engage meaningfully with families and informal supporters where appropriate.

Despite frustrations, carers also acknowledged examples of good practice and supportive professionals within mental health services. Several attendees noted that they had seen gradual improvements in carer involvement and listening exercises within parts of South London and Maudsley NHS Foundation Trust (SLAM), particularly in Lambeth.

Updates on Carer Involvement and Support Activities

The group received updates from carers and representatives involved in local mental health engagement work and carers’ organisations.

Carers Week Activities

Karen from Carers Hub Lambeth shared details of upcoming Carers Week activities, including:

  • outreach events,
  • wellbeing sessions,
  • information stalls,
  • and activities for both adult and young carers.

The events aim to provide carers with opportunities for support, networking, practical advice, and wellbeing activities.

Here is more info on Carers Week 2026

https://www.carersweek.org/about-carers-week/latest-news/posts-folder/2026/january/carers-week-dates-for-2026

SLAM and Carer Involvement

There was also discussion around changes and developments within SLAM involvement structures, including:

  • continuation of family and carers meetings,
  • changes to involvement leads,
  • and ongoing reviews of the involvement register.

Attendees reflected positively on the increasing recognition of carers’ voices in some forums and clinical meetings, while acknowledging that there is still much work to do to ensure consistent involvement across all boroughs and services.

Guest Presentation: Mapping Patient Support Networks

The second half of the meeting focused on a presentation from Dr Anna De Simone, GP and Associate Professor of Primary Care at Queen Mary University of London.

Anna introduced a proposed research project exploring how healthcare systems might better understand and map patients’ support networks using electronic health records and social network tools.

The research proposal focuses particularly on patients with long-term conditions such as COPD (Chronic Obstructive Pulmonary Disease), many of whom also experience multiple additional health conditions and varying levels of social isolation.

The Core Idea

Anna explained that while healthcare professionals can currently access limited information such as next of kin or household members, they often lack a fuller understanding of:

  • who actually supports the patient,
  • how reliable that support is,
  • whether support networks are connected or fragmented,
  • and how socially isolated a patient may be.

The proposed research would explore whether creating visual “maps” of support networks could help:

  • improve care planning,
  • reduce crises,
  • improve coordination between services,
  • and enhance patients’ quality of life.

The project would also examine how social prescribing, community services, online support groups, and carers fit into these wider support networks.

Carers’ Feedback on the Research Proposal

The discussion following Anna’s presentation was extremely rich and constructive, with carers offering both enthusiasm and important cautionary perspectives.

Strong Support for the Concept

Many attendees felt the project addressed an important gap in healthcare planning. Several carers spoke about how informal support networks had been essential to helping them or their loved ones survive periods of crisis.

Participants agreed that professionals often underestimate the role played by:

  • friends,
  • neighbours,
  • online communities,
  • peer groups,
  • and unpaid carers.

The ability to visualise these networks was seen as potentially valuable for both professionals and patients themselves.

Importance of Non-Traditional Support Networks

A strong theme throughout the discussion was that support does not always come from family.

Some carers explained that family relationships can sometimes be unsafe or abusive, and that support may instead come from trusted friends, neighbours, carers’ groups, or online communities.

The group stressed that any future system should avoid assuming that family automatically equals safety or support.

Online Communities and Digital Support

Participants also highlighted the increasing importance of online support systems.

Several carers explained that:

  • Zoom groups,
  • Facebook communities,
  • online peer support,
  • and digital communication
    can provide essential social connection, especially for disabled or isolated people.

One participant noted that online support networks had directly helped them access practical support and reduce isolation when physical mobility was limited.

At the same time, carers cautioned that not everyone has equal access to digital services. Concerns were raised about:

  • digital exclusion,
  • accessibility barriers,
  • lack of digital skills,
  • and the risk of widening inequalities.

The importance of offering both digital and non-digital forms of support was strongly emphasised.

Privacy, Consent, and Mental Health

Carers also discussed potential challenges around privacy and consent, particularly for people experiencing paranoia or severe mental illness.

Some attendees noted that patients may not always feel comfortable sharing details about their social networks, and that trust and safeguarding would need to be central to any future system.

There was discussion about the delicate balance between:

  • confidentiality,
  • safety,
  • carer involvement,
  • and patient autonomy.

Role of Social Prescribers

The group generally agreed that social prescribers could play an important role in helping patients map support networks, because they often have more time and a stronger focus on community support than standard GP appointments allow.

However, concerns were raised about long-term funding and sustainability for social prescribing services.

Looking Ahead

Anna thanked the group for their detailed feedback and explained that carers’ insights would help shape the next stage of the research proposal before submission later this year.

There was strong interest from attendees in remaining involved should the project move forward, particularly around future patient and public involvement opportunities.

The meeting once again demonstrated the depth of knowledge, experience, and expertise held by unpaid carers. The discussion reflected not only the challenges carers continue to face, but also the importance of ensuring carers are recognised as essential partners in both healthcare delivery and future research.

National Ethnic mental health Carer Forum : March Update 2026

Chaired by Matthew McKenzie – Carer Activist

The March session of the National Ethnic Mental Health Carer Forum brought together carers, researchers, NHS professionals and community organisations for a conversation that felt both familiar and urgent.

Chaired by Matthew McKenzie, the forum stayed rooted in what it does best: creating a national grassroots space where lived experience meets systems, and where difficult truths are not avoided.

The agenda reflected that balance clearly:

  • 10:35 – Professor Saffron Karlsen (University of Bristol)
  • 11:20 – King’s College London (Phoebe Averill & team)
  • 11:50 – Parliamentary and Health Service Ombudsman
  • 12:00 – Thomas Ince – Universal Care Plan

Racism and Mental Health: Naming What We Already Know

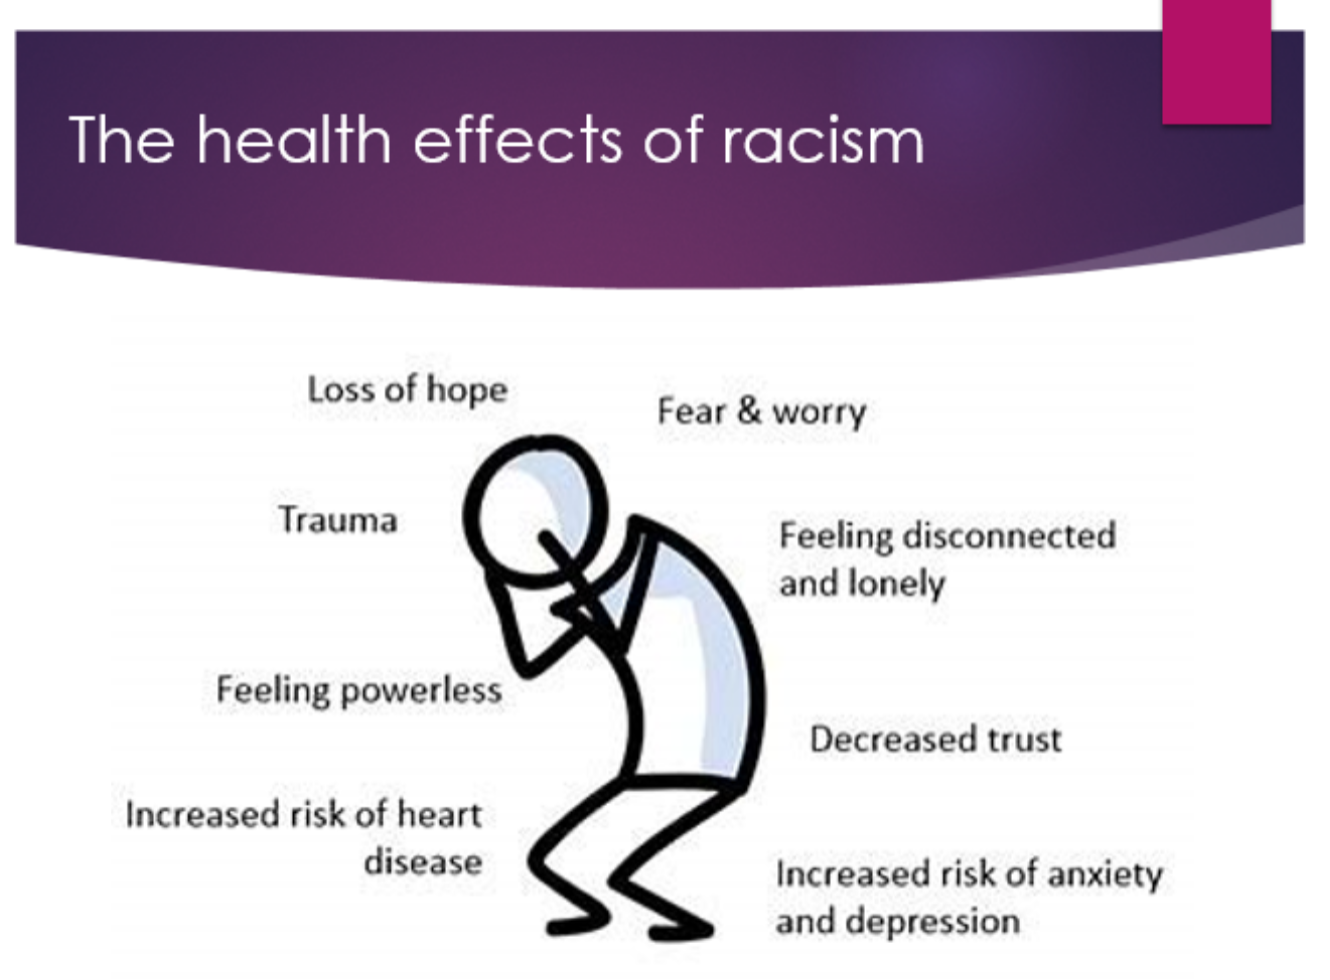
Professor Saffron Karlsen opened the forum with a presentation that didn’t just describe inequality it explained how it is produced, sustained, and experienced in everyday life.

Drawing on over 30 years of research, Professor Saffron Karlsen is a sociologist at the University of Bristol whose research examines how racism and social inequality affect health, particularly within ethnic minority communities.

she spoke about racism not as a single act or incident, but as something woven into the fabric of society. It operates quietly and persistently, through institutions, through policies, through media narratives, and through the ways people interact with one another. The effect is cumulative. It builds over time, shaping not just opportunities, but health itself.

What made the presentation particularly powerful was how it connected these structural ideas to real human consequences. Racism was described as something that works on multiple levels at once: from overt abuse or violence, to the less visible but equally damaging experience of simply knowing that you live in a society where you may be treated unfairly. That awareness alone carrying the expectation of discrimination creates a constant undercurrent of stress and anxiety.

She explained how this stress doesn’t just sit in the mind. It translates into physical outcomes. People exposed to racism are more likely to experience anxiety, depression, and long-term distress, but also physical health inequalities such as cardiovascular disease. These outcomes are often misunderstood or misrepresented. Too frequently, they are explained away as lifestyle issues diet, exercise, personal choice without recognising the deeper social conditions that shape those behaviours in the first place.

A particularly striking part of the presentation focused on how people respond to these pressures. When individuals feel powerless to change their circumstances, they may turn to coping mechanisms smoking, drinking, or withdrawing from services. These responses are then judged in isolation, rather than understood as part of a wider context. In this way, the system not only fails to address the root causes but can end up reinforcing blame on the individual.

Perhaps the most important insight came when the discussion turned to healthcare itself. Even when services are available, they are not always experienced as safe or trustworthy. Saffron shared research showing that people may avoid seeking help not necessarily because of direct negative experiences, but because of what they have seen and heard about racism more broadly. The perception of risk becomes enough to keep people away.

One example described a woman who, during the COVID period, chose to avoid hospital care entirely. Her decision was shaped by what she had seen in public discourse and online reactions to racial justice movements. It left her feeling that she could not trust how she would be treated. This kind of anticipatory fear of not being treated with dignity or fairness adds another layer of stress to an already difficult situation.

The presentation also challenged the way healthcare systems understand illness. Many services still operate within a narrow biomedical framework, focusing on symptoms and diagnoses while overlooking the social realities that contribute to them. For people from marginalised communities, this can lead to experiences where their perspectives are dismissed or misunderstood. They may try to explain how racism, housing, poverty, or life circumstances have shaped their health, only to find those explanations sidelined.

This is where the concept of “epistemic injustice” becomes important, although Saffron didn’t dwell on jargon, the meaning was clear. It is about whose knowledge counts. When patients and carers are not listened to, or when their experiences are not taken seriously, care becomes something done to them, rather than with them. For many, this is not just frustrating it is re-traumatising.

Professor Saffron also showed a video – Nilaari delivering hope A community mental health provider for people of colour, which you can watch below.


Q&A Section : From Evidence to Frustration

1. “You’ve explained the problems, but what are the solutions?”

Answer:
Saffron acknowledged that addressing racism at its root is complex and long-term, but highlighted practical steps:

  • Services must be co-produced with people who have lived experience
  • Communities need to be actively involved in decision-making spaces
  • Grassroots and voluntary organisations should be:
    • properly funded
    • meaningfully included in policy and service design

She emphasised that change should be done with communities, not to them, and that learning from effective third-sector approaches is key.


2. “Do you look at drug and alcohol use as part of racism-related issues?”

Answer:
Yes, but not in the way systems often frame it.

Saffron explained that:

  • Substance use is often a response to difficult life experiences, including racism and poverty
  • Systems tend to treat it as an individual problem, rather than understanding the wider causes
  • These behaviours can reflect a lack of:
    • support
    • options
    • alternative coping mechanisms

She stressed the importance of shifting away from blame and towards understanding context.


3. “Is trauma-informed care part of the solution?”

Answer:
Trauma-informed care is important, but not sufficient on its own.

Saffron highlighted that:

  • Current models of trauma-informed care can be too narrow
  • They often fail to fully account for:
    • systemic racism
    • structural inequalities
  • Services also need to recognise that they themselves can contribute to trauma

She suggested that trauma-informed approaches must be:

  • culturally sensitive
  • shaped by different communities’ understandings of trauma

4. “What do you mean by ‘racism is a virus’?”

Answer:
Saffron used this idea as a metaphor.

She explained that:

  • Racism spreads and reproduces across society, much like a virus
  • It moves through:
    • institutions
    • policies
    • social interactions
  • It grows and reinforces itself over time

At the same time, she used this idea to challenge overly individualised thinking—highlighting that racism is structural, not just personal.


King’s College London: When Crisis Care Comes Too Late presented by Phoebe Averill.

After the earlier discussion on racism and inequality, the presentation from King’s College London brought the conversation into something more immediate what actually happens when someone reaches crisis point and needs urgent mental health support.

Phoebe Averill and her team focused on pathways under the Mental Health Act, but what emerged wasn’t a technical discussion. It was a picture of a system that often struggles at the exact moment it is supposed to respond.

They began by looking at the period just before crisis. In many cases, there are early warning signs. Carers and families notice changes subtle at first, then more obvious. They often try to raise concerns early, hoping intervention might prevent things from escalating. But too often, those early signals are not acted on.

By the time the system responds, the situation has already deteriorated.

The research highlighted that delays are not caused by a single issue, but by a combination of pressures within the system. These include:

  • shortages in hospital beds
  • fragmented coordination between services
  • breakdowns in communication across teams

While these explanations are familiar, the impact of them feels anything but routine. During the waiting period, people do not remain stable. They become more unwell, more distressed, and more at risk. What could have been addressed earlier becomes a crisis that is harder to manage.

One of the most striking parts of the presentation was the focus on what happens in that gap between “something is wrong” and “help arrives.” That space is where much of the pressure shifts onto carers.

Carers described being left to manage situations that are escalating in real time. They are expected to keep someone safe, to monitor behaviour, and to absorb the emotional weight of what is happening all while waiting for services to respond. In some cases, this can last days or even weeks.

This isn’t a formal role, and it’s not one carers are prepared for. It’s something they step into because there is no alternative.

The consequences of these delays don’t end when care finally arrives. By that point, the impact can already be significant. The research pointed to outcomes such as:

  • worsening mental health leading to longer hospital stays
  • increased risk of avoidable harm during the waiting period
  • disruption to housing, employment, and relationships

In other words, the delay itself becomes part of the problem, shaping what happens next.

Another important thread running through the presentation was the role of carers’ knowledge. Carers are often the first to recognise when something is changing. They understand patterns, triggers, and early warning signs in a way that professionals may not see immediately. Yet this insight is not always taken seriously or acted upon.

The result is a system that tends to respond late rather than early intervening at crisis point, rather than preventing it.

The KCL team were clear that their research is trying to address this gap. They spoke about building a lived experience advisory group and involving carers and service users directly in shaping the work. There was a clear intention to move beyond observation and towards something more collaborative, where lived experience informs how the research develops.

At the same time, there was a quiet recognition in the room that much of this is not new. Similar issues have been raised repeatedly over the years. The difference here was not the discovery of the problem, but the clarity of where it sits in that critical moment where response is needed, and the system is slow to act.

Placed alongside the earlier discussion on racism, this presentation added another layer of understanding. It showed how broader inequalities are not abstract—they play out in very real ways at the point of crisis. Where trust is already fragile, delays make it harder to engage. Where carers are already stretched, the system’s response can increase that pressure rather than relieve it.

By the end of the session, one idea stood out clearly: this is not just about whether care is available. It is about whether it comes at the right time, whether the right people are listened to, and whether the system is able to act before situations reach breaking point.


Parliamentary and Health Service Ombudsman: When Accountability Feels Out of Reach

The next presentation of the forum came from the Parliamentary and Health Service Ombudsman team, who joined to explain how carers and families can raise concerns when NHS care goes wrong.

On the surface, this was a session about process how complaints move through the system and when the Ombudsman becomes involved. But as the discussion unfolded, it became clear that this was really about something deeper: whether accountability is genuinely accessible to carers in practice.

The team described their role as an independent body that steps in once local complaints processes have been completed. In theory, the pathway is clear. Before approaching the Ombudsman, people are expected to go through several stages:

  • raise concerns with the service directly
  • receive a formal response, often referred to as the “final response letter”
  • only then escalate the complaint for independent review

What sounds straightforward on paper quickly became more complex when viewed through lived experience.

Carers shared how difficult it can be to even reach that final stage. The process can take months, sometimes longer, and often requires sustained effort just to keep it moving. Following up, chasing responses, and navigating unclear communication becomes part of the experience.

One comment in the chat captured this reality clearly:

“It can be hard to get to the point of getting a final outcome letter… the amount of advocacy and chasing that needs to happen…”

Another highlighted how far removed the process can feel from everyday awareness:

“It takes far more than 12 months to even come into awareness…”

In response, the Ombudsman team acknowledged that delays particularly at the final response stage are common. They explained that in some cases, where delays are extreme, they may contact organisations directly, and they encouraged people to use their helpline for guidance when processes stall.

But even with that support, there was a sense in the room that the system places a significant burden on those trying to access it. By the time someone considers making a complaint, they are often already dealing with the aftermath of a difficult experience. Adding a lengthy and sometimes frustrating process on top of that can feel overwhelming.

The conversation also turned to accessibility. Questions were raised about language, digital access, and the assumptions built into how information is shared. Not everyone engages with systems in the same way, and not everyone finds it easy to navigate written guidance or formal processes.

Participants pointed out that some communities may never reach the complaints stage at all—not because issues don’t exist, but because the pathway itself is difficult to access.

This was reflected in a simple but powerful comment:

“We are assuming that everyone reads…”

There were also wider reflections about how systems could better meet people where they are, including:

  • making information available in more accessible formats and languages
  • reaching people through community networks, not just formal channels

Even within this practical discussion, the themes from earlier in the forum remained present. Trust, accessibility, and lived experience all shaped how people understood the complaints process.

Placed alongside the earlier presentations, this session added an important dimension. If the system fails as described in the discussions on racism and crisis care—then the ability to challenge that failure becomes critical. But if the route to accountability is difficult to navigate, many experiences may never be formally recognised.

What emerged was not a rejection of the Ombudsman’s role, but a recognition of the gap between what exists and what is accessible.

Because accountability is not just about having a process in place.
It is about whether people can realistically use it especially at a time when they may already be stretched, exhausted, and navigating multiple pressures.


Universal Care Plan and Carer Contingency Planning Update

The final contribution to the forum came from Thomas Ince, introducing the Universal Care Plan often referred to as UCP. After the earlier discussions on racism, crisis care, and accountability, this felt like a shift towards something more practical: what the system is trying to build in response to the gaps carers have been describing.

At its core, the Universal Care Plan is a digital tool designed to allow people to record and share information about their care. It sits within the NHS App and is intended to bring together health, social care, and voluntary services around a shared understanding of a person’s needs and preferences.

Thomas described how the system has evolved over time. It began with a focus on end-of-life care, making sure that a person’s wishes could be accessed quickly by professionals such as ambulance crews. It then expanded into areas like sickle cell crisis planning and is now being extended further to cover a wider range of conditions and situations.

The direction of travel is clear: moving from a professionally controlled system towards something more person-owned, where individuals can enter their own information and shape how their care is understood.


A Tool That Centres “What Matters to You”

One of the key features Thomas highlighted was a section within the plan that allows people to describe themselves in their own words. Rather than being defined only by diagnosis or clinical notes, individuals can record what matters to them information that can then be seen by anyone involved in their care.

In principle, this is a shift towards more personalised and human-centred care. It offers a way to capture context, preferences, and lived experience in a system that often reduces people to categories.

But for this forum, the most significant element was something more specific.


The Carer Contingency Plan

Thomas introduced a feature that immediately resonated with the group: the carer contingency plan.

This allows carers to record what should happen if they are suddenly unable to provide care. For example:

  • if they become unwell or need urgent medical attention
  • if there is a sudden change in their circumstances

In those situations, the system can alert professionals to the fact that someone is dependent on that carer and provide information about what support is needed.

For many carers, this addressed a very real and often unspoken concern:
what happens to the person they care for if something happens to them?

The idea that this information could be visible across services—rather than held informally or not at all felt like a meaningful step.


From Concept to Reality: The Challenge of Engagement

While the tool itself was broadly welcomed, the discussion quickly moved beyond what it does to how it will actually be used.

Thomas was open about the current stage of development. Although the system is available, it remains largely driven by professionals, with limited public awareness. One of the key aims now is to shift towards wider engagement encouraging people to take ownership of their care plans and input their own information.

This raised an important question in the room: how do you introduce a digital solution into communities where trust in services is already fragile?

Participants pointed out that many people particularly from ethnic minority backgrounds—do not engage easily with primary care systems. If the entry point to the Universal Care Plan is through those same systems, there is a risk that the people who could benefit most may not use it at all.

Suggestions began to emerge organically from the group, reflecting a more community-led approach:

  • working through carer centres, peer groups, and local networks
  • engaging cultural organisations and community leaders
  • using spaces where trust already exists, rather than relying solely on formal channels

There was a clear sense that communication could not be an afterthought. It needed to be built into the design of how the tool is introduced.


Language and Accessibility: A Tension Exposed

One of the most striking moments in this section came when language accessibility was discussed.

At present, the NHS App and therefore the Universal Care Plan is only available in English (and Welsh). Thomas acknowledged that this is a limitation and that while there are conversations about future solutions, no immediate changes are in place.

This prompted a strong reaction from participants. There was frustration that a tool described as “universal” could exclude large sections of the population from the outset. For some, this was not just a technical issue but a reflection of a wider pattern—systems being designed without fully considering the diversity of the communities they serve.

It brought the discussion back to a familiar theme from earlier in the forum:
inclusion cannot be added later, it has to be built in from the beginning.


A Step Forward With Conditions

Despite these concerns, there was recognition that the Universal Care Plan has real potential.

The idea of having:

  • shared, accessible information across services
  • visibility of carers and their responsibilities
  • a contingency plan that reduces risk in emergencies

addresses issues that carers have been raising for years.

But the conversation made it clear that the success of the tool will depend on more than its functionality. It will depend on whether people:

  • know about it
  • trust it
  • can access it
  • and feel that it reflects their needs and realities

Without that, there is a risk that it becomes another well-intentioned solution that doesn’t reach the people it was designed for.


Placing It in the Wider Conversation

Coming at the end of the forum, this presentation connected in an important way to everything that had been discussed earlier.

Where Saffron’s presentation explored the structural roots of inequality, and the KCL research showed how system delays affect people in crisis, the Universal Care Plan represented an attempt however early to respond to those issues in practice.

But it also revealed the ongoing challenge.

Because even when new tools are introduced, they are still shaped by the same system dynamics:
questions of trust, access, communication, and inclusion do not disappear they simply take new forms.

The Power of Lived Experience and Carer Voices in Healthcare: A Conversation with Hannah Codogin

By Matthew McKenzie – Carer activist

In a recent interview, Matthew McKenzie sat down with Hannah Codigan, a palliative care nurse who brings a unique perspective to healthcare, not only as a professional but also as someone with lived experience of serious mental illness. Together, they explored the importance of recognising unpaid carers and embedding lived experience voices in the design and delivery of healthcare services.

Caring Beyond the Patient

Hannah shared how her role in hospice care extends beyond patients to include families and carers who often struggle without recognition. She emphasised that carers need as much emotional and practical support as the people they care for, noting how time pressures in nursing can make it difficult to truly listen to their experiences.

Continue reading →