As I continue developing my poetry collection Unpaid, Unseen and Yet Unbroken: Poetry about Ethnic Mental Health Carers, I wanted to share another poem from the collection called Language as Comfort.
This is Poem 30 and explores something that can easily be overlooked when we talk about involvement in mental health services: the comfort and belonging that can come from being able to communicate in your own language.
Watch the poem below.
For many ethnic minority carers, language is about much more than translating individual words. Our mother tongue can be connected to family, culture, identity, memory and a feeling of safety.
When language becomes part of carer inclusion
Language barriers can affect how confidently carers participate in assessments, consultations and discussions about the person they support.
This is why one part of the poem asks services to record a carer’s language needs:
A carer should not have to start again at every appointment, repeatedly explaining how they need information to be communicated.
This connects strongly with the Patient and Carer Race Equality Framework (PCREF). If we want meaningful involvement from diverse communities, we need to think about whether our usual ways of communicating actually enable people to participate.
The poem ends with the idea of language helping someone to “break free from this cage”.
For me, that is the central message of Language as Comfort. Being understood can create confidence. Being able to communicate can create involvement. And recognising someone’s language can help create a sense of belonging.
Language should not be another barrier between carers and mental health services.
It can instead become part of the bridge.
Poem 30 from the developing collection Unpaid, Unseen and Yet Unbroken: Poetry about Ethnic Mental Health Carers.
As I continue developing my poetry collection Unpaid, Unseen and Yet Unbroken: Poetry about Ethnic Mental Health Carers, I wanted to share another poem from the collection called Fear Has Roots.
The poem explores something I feel mental health services need to understand more deeply: mistrust does not always begin with the person standing in front of you.
Sometimes it has a history.
A carer may have experienced years of being dismissed, misunderstood or having their concerns minimised. They may have watched other carers from their community struggle to be heard. Experiences of discrimination can also travel through families and communities, influencing how safe people feel when approaching services.
Fear Has Roots explores what happens when those experiences begin to change the way a carer communicates.
The carer starts choosing their words carefully. They worry about appearing angry. They fear being labelled “difficult” or “aggressive”. Even when trying to advocate for someone they love, they may feel that one wrong word could change how professionals see them.
One section of the poem says:
For me, this is particularly important when thinking about ethnic minority carers and the Patient and Carer Race Equality Framework (PCREF).
If services want to build trust with communities, it is not enough simply to ask why somebody mistrusts the system. We also need to ask what happened before that mistrust developed.
Listening to what sits behind the fear
The poem is not anti-professional. In fact, its opening line deliberately makes that clear:
“Fear has roots, I am not anti-professional.”
Instead, it asks professionals and services to become curious about the experiences behind a carer’s behaviour.
Repeated dismissal can wear somebody down. Discrimination can leave lasting memories. Feeling judged when advocating for a loved one can make a carer more cautious the next time they enter a meeting, ward or assessment.
This is why culturally responsive carer involvement matters.
We should not only hear what carers are saying. We should also understand the history, culture and experiences that may sit behind their words.
Fear has roots.
Mistrust has a history.
And perhaps listening is one of the places where rebuilding trust can begin.
Fear Has Roots is part of my developing poetry collection Unpaid, Unseen and Yet Unbroken, which explores race, culture, identity, inequality, resilience and the experiences of ethnic minority unpaid mental health carers.
Think Tenacity Academy CIC is hosting another important Making Time for Black Mental Health event in London.
The free racial trauma seminar will take place on:
Wednesday 23 September 2026 3:00 pm–9:00 pm Cottons Shoreditch, 321 Old Street, London EC1V 9LE
The event will provide a culturally informed space to explore racial trauma, mental health and wellbeing within Black communities. It will also create opportunities for people with lived experience, carers, professionals and community organisations to connect and learn from one another.
I attended a previous Making Time for Black Mental Health event and saw how valuable these community-led spaces can be. They enable conversations about race and mental health to take place in an environment where people feel understood, represented and supported.
As a lived experience Black mental health carer and advocate, I know that racial trauma can affect not only individuals but also families and unpaid carers. We need more culturally responsive spaces that recognise these experiences and make it easier to discuss mental health without fear, judgement or stigma.
The event is free to attend, but capacity is limited to approximately 45 places, so early booking is strongly recommended.
A related Racial Trauma Group Support event is also advertised for Thursday 1 October in Notting Hill.
By Matthew McKenzie – Chair of ethnic MH Carer forum / Chair of Cancer Carergiver group
I was recently sent information about an important cancer care project being led by Learning Disability England in partnership with the Race Equality Foundation which is funded by Macmillan Cancer Support.
The project aims to improve cancer care for people with learning disabilities from Black, Asian and minoritised ethnic communities. A working group is being established involving self-advocates, family members and friends who have experience of cancer.
By Matthew McKenzie – Carer Activist and Carer Advocate
On 8 September 2026, I had the honour of attending the DUALITY event at King’s College London, held at Bush House.
The event was a research and public/community engagement event connected to the INTERCEPTION study, based in King’s Department of Global Health & Social Medicine, within the School of Global Affairs / Faculty of Social Science & Public Policy.
There was a packed agenda, which I have shown below.
Registration, refreshments and photo exhibition — Attendees arrived, had refreshments and had an opportunity to look around the community photography exhibition.
Welcome and introduction to DUALITY — The organisers introduced the event and its focus on ageing, ethnicity, health and experiences of living with multiple long-term conditions.
Research Panel: Ethnicity, Ageing and Health — Researchers discussed work exploring inequalities and experiences at the intersection of ethnicity, ageing, health and multiple long-term conditions.
King’s Sport & Wellness energiser — Attendees were invited to take part in accessible seated stretches and movement exercises.
Human Library — Attendees could “borrow” Living Books for short conversations, hearing personal stories intended to build understanding, foster empathy and challenge assumptions. My Living Book was “The Carer They Didn’t See.”
Community information booths — Organisations and community representatives provided information and resources. This was also where I supported the Carers UK stall.
DUALITY Photography Exhibition — Photographs used visual storytelling to explore support, health, ageing and lived experience. My photograph “The Carer They Didn’t See” was included in the exhibition.
Photography Competition Awards — Winners of the DUALITY Photography Competition were announced, with “The Carer They Didn’t See” selected as one of the winning entries.
Creative performance — The programme included a creative lived-experience performance exploring identity, Caribbean heritage, racism, family, memory and culture.
Keeping Fit with Multiple Long-Term Conditions — This discussion brought professional and lived-experience perspectives together to explore chronic conditions, exercise, confidence and wellbeing.
Dinner and networking — The evening concluded with food and an opportunity for attendees, researchers, community groups and people with lived experience to connect.
This was quite a different event for me. I have attended many conferences, workshops and involvement events over the years as an unpaid carer, carer advocate and speaker. This time, however, I wasn’t simply attending or presenting.
I became a book.
More specifically, I became a Living Book as part of the event’s Human Library.
My title was:
The Carer They Didn’t See
And by the end of the evening, that title would take on another meaning I hadn’t expected.
What was the DUALITY event?
DUALITY brought together research, lived experience, creativity, photography, health and conversations about ageing and multiple long-term conditions.
What I particularly appreciated was the emphasis on people’s experiences rather than simply presenting research about people.
Throughout the event there were presentations, discussions, creative displays and opportunities for people to connect with one another.
I also ran the Carers UK Stall along with other things I use to raise unpaid carer awareness
Photography was also an important part of the project. Participants from different parts of the world had taken part in workshops exploring photography as a way of capturing support, people’s inner and outer worlds, ageing and multiple long-term conditions.
But one of the most interesting parts for me was the Human Library.
When people become books
The Human Library turns the idea of a conventional library on its head.
Instead of borrowing a book from a shelf, you borrow a person.
The organisers explained that the Human Library is intended to foster empathy, challenge prejudice and provide a safe space in which people can ask questions of someone they might not ordinarily meet. Visitors browse the available titles and then spend a short period listening to that person’s story and having a conversation with them.
There were several Living Books available, each representing very different experiences.
My book was called The Carer They Didn’t See.
My short description read:
“I was a carer nobody counted, until grief became words, and words became my way to say: we’re here, and we matter.”
That sentence says a great deal about why I continue campaigning around unpaid carers.
For years I supported my mother, who lived with serious mental illness. Like many unpaid carers, much of what I did happened quietly and behind closed doors.
There was no uniform.
There was no job title.
Often there wasn’t even recognition that I was a carer.
Yet the responsibility was very real.
Being “read”
Being a Living Book is quite different from giving a presentation.
When presenting at a conference, I usually have slides, a topic and a limited amount of time in which to make particular points.
The Human Library was much more personal.
Someone chooses your “book” because something about its title interests them. They sit with you, listen and can ask questions.
That creates a different kind of conversation.
It also made me think about how powerful lived experience can be when people are given the space not merely to tell their story, but to have somebody genuinely listen to it.
The organisers themselves acknowledged that hearing stories we would not normally encounter can sometimes be challenging and thanked the Living Books for making the time and space for those conversations.
For unpaid carers, I think that is particularly important.
We spend a great deal of time discussing services, policies, strategies and systems. Those things matter enormously.
But behind every carer statistic is a human story.
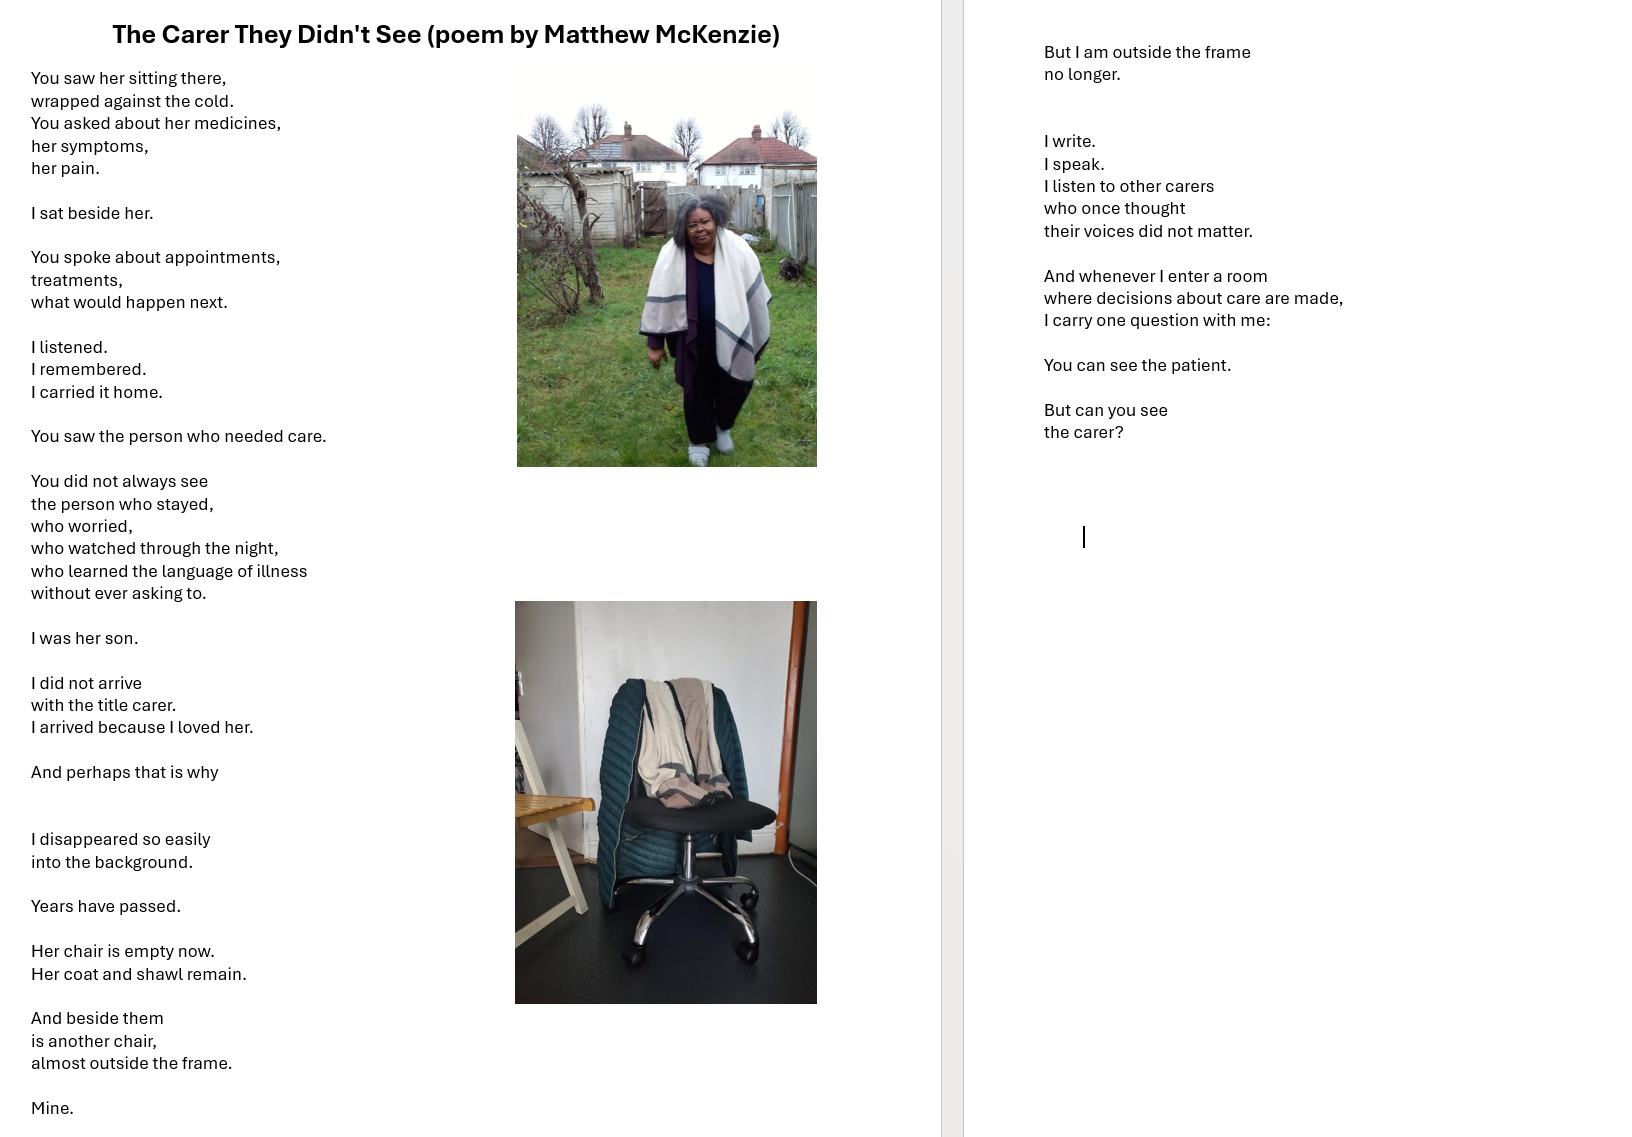
The photograph of an unseen carer
There was another part of the event that became especially significant for me.
I had also entered a photograph into the DUALITY community photography competition.
The photograph looks deceptively simple.
It shows my mother’s coat and shawl resting on a chair. My own chair sits partly outside the frame.
That positioning was deliberate.
My mother’s chair occupies the centre because she was the person receiving support. My own chair sits towards the edge because I wanted to represent something that many unpaid carers experience:
We are always there, but we are not always seen.
I also deliberately kept the ordinary home environment visible.
Caring doesn’t only happen in hospitals, clinics and professional environments.
A huge amount of caring happens quietly in people’s homes.
There may be no audience to see the difficult nights, the worry, advocacy, appointments, emotional support or constant vigilance.
But the carer is there.
When photography becomes lived experience
One thing I enjoyed about the photography project was learning that a powerful photograph doesn’t necessarily require expensive equipment or an elaborate setting.
The workshops explored techniques including framing, symbolic composition, symmetry, colour and other approaches to visual storytelling.
For me, however, the emotional meaning of the photograph mattered most.
The coat and shawl belonged to my mother.
The empty chair therefore represents much more than furniture.
It connects the photograph directly to my own experience of caring, bereavement and the work I now do to raise awareness of unpaid carers.
During the judging discussion, I was delighted to hear The Carer They Didn’t See specifically mentioned as one of the photographs demonstrating different dimensions of support.
I wasn’t expecting what happened next.
Winning the DUALITY Photography Competition
When the winners were announced, my name was called.
The Carer They Didn’t See had been selected as one of the winning entries.
I received a medal engraved:
WINNER Matthew McKenzie Duality Photo Competition 2026
I was very surprised.
I won a four-week personal training block with a coach at the King’s Sports and Wellness Centre in Waterloo.
For me, though, the most meaningful prize was the recognition of the story behind the photograph.
It meant that an image representing an unpaid carer’s experience had been noticed.
And perhaps there is some irony in that.
I created a photograph called The Carer They Didn’t See.
And people saw it.
Listening to other lived experiences
The evening was certainly not only about my own story.
One of the strengths of DUALITY was hearing from people with very different experiences.
There was discussion about musculoskeletal conditions, multiple long-term conditions, physical activity, persistent pain and the importance of taking a more holistic approach to people’s health.
I was particularly struck by the lived-experience discussion about fibromyalgia.
One speaker described how developing chronic pain changed her life and even affected her sense of identity. She spoke about a long and frustrating journey through healthcare before receiving a diagnosis, and about sometimes feeling that her symptoms were being questioned or invalidated.
She also described how movement and supported exercise helped her reconnect with her body, understand her limits and rebuild confidence.
One comment particularly fitted the wider theme of the evening: we often cannot see what another person is experiencing.
Invisible conditions and invisible caring have something important in common.
Culture, identity and memory
Another powerful part of the evening explored culture, memory and identity.
We heard personal reflections on growing up in London’s East End, experiences of racism, Caribbean heritage, family, music and the ways culture can become a source of strength and protection.
That fitted beautifully with the idea of DUALITY.
From grief into creativity
Since losing my mother, I have increasingly used writing, poetry, blogging and other creative approaches to explore my experiences of unpaid caring.
Creativity allows me to communicate things that sometimes don’t fit neatly into a presentation or policy document.
A photograph can do the same thing.
A chair.
A coat.
A shawl.
An empty space.
For somebody else, these may simply be everyday objects.
For me they contain memories of caring.
And when placed together within a frame, they say something about the millions of unpaid carers whose contribution can remain just outside society’s field of vision.
Recognition as a Living Book
I was also very grateful to receive a Certificate of Appreciation recognising my contribution as a Living Book at the DUALITY Human Library.
That certificate and the photography medal represent two quite different parts of the same day.
One recognises telling a story.
The other recognises showing a story.
Both were ultimately about lived experience.
The carer they finally saw
I left King’s College London thinking again about the title I had chosen:
The Carer They Didn’t See.
For many years, that description could have applied to me.
It could still apply to countless unpaid carers today.
They may be sitting beside someone in hospital.
They may be managing a crisis at home.
They may be trying to navigate mental health services.
They may be a son, daughter, parent, sibling, partner, friend or neighbour.
And sometimes they don’t even recognise themselves as carers.
Events such as DUALITY provide another way of making those experiences visible.
But people’s stories matter too.
I went to King’s College London expecting to share mine as a Human Book.
I didn’t expect to leave wearing a gold medal for a photograph inspired by that same caring journey.
By Matthew McKenzie – Chair, National Ethnic Mental Health Carers Forum
The August meeting of the National Ethnic Mental Health Carer Forum brought together unpaid carers, NHS leaders, healthcare professionals, academic researchers, and voluntary sector advocates from across the country. The session provided a vital space to address race equity, systemic racism, lived experience, and ongoing research into minoritised caring experiences.
Matthew McKenzie opened the meeting by welcoming attendees and reinforcing the core purpose of the national forum. He reflected on how the platform has grown into a crucial space where family carers can directly challenge health structures, influence decision-makers, and learn about national policy developments such as the Patient and Carer Race Equality Framework (PCREF). Matthew acknowledged that while discussions around institutional racism and health inequalities can be heavy and emotional, the forum remains a safe, respectful, and healing space dedicated to driving real, actionable change across the NHS.
Minute of Silence: Professor Jason Ardey
The forum opened with a poignant minute’s silence led by Debbie Best in honour of the life, legacy, and memory of Professor Jason Ardey following his passing.
Members paused to reflect on his landmark contributions to racial equality, education, and social justice. His legacy of challenging institutional barriers and amplifying minoritised voices continues to inspire the core work and mission of the forum.
Reflections on Race Equality: Norfolk and Suffolk NHS Foundation Trust (NSFT)
Speakers: Cath Byford (Deputy Chief Executive / Chief Nurse / Director of Patient Experience) & Annie (PCREF Carer Lead)
Cath Byford opened the trust’s update by offering an open and unvarnished reflection on NSFT’s ongoing race equity journey. Acknowledging that the trust has faced significant scrutiny and structural challenges over recent years, Cath emphasized that building genuine trust with minoritised communities requires moving beyond policy statements to deliver measurable, lasting systemic change. She explained that over the past 18 months, NSFT has embarked on a deliberate path to rebuild its patient experience framework, ensuring that health equity, anti-racism, and lived experience are embedded into every layer of clinical governance and strategic planning.
PCREF Carer lead Annie brought a vital lived-experience perspective to the presentation, sharing how the trust is working to bridge the gap between executive decision-making and the everyday realities of unpaid family carers. Together, they outlined the core pillars driving NSFT’s current equity transformation:
Dedicated Health Equity Team & Clinical Reform: The trust has invested heavily in establishing a specialist Health Equity team, created to audit clinical pathways and directly confront institutional disparities. The team’s operational focus is centered on dismantling disproportionate clinical interventions, specifically working to significantly reduce the use of physical and chemical restrictive practices, address the over-representation of Black and minority ethnic service users detained under the Mental Health Act, and monitor and reduce the disproportionate application of Community Treatment Orders (CTOs).
Diversifying Governance & Locality Councils: Cath shared candidly that an internal review of the trust’s governance structures revealed a stark under-representation of global majority voices across its five locality councils. Recognizing that local health strategies cannot succeed if key decision-making bodies remain ethnically unrepresentative, NSFT has launched targeted community outreach initiatives designed to recruit diverse community members, carers, and experts by experience onto these councils to ensure grassroot priorities shape service delivery.
Workforce Transformation & Reciprocal Mentorship: Highlighting broader organizational culture, Cath detailed how workforce race equity has been integrated into the trust’s 12 major transformation programmes. A central highlight of this work is the Transformational Reciprocal Mentorship Programme, coordinated by Ethan Charles, which was recently recognized nationally for healthcare excellence. The initiative pairs senior trust executives and board members with staff members from minoritised backgrounds in a reciprocal learning partnership, helping leadership understand systemic workplace barriers while creating clear pathways for career progression and equity across the trust.
Questions and Discussion
Q1. How is Norfolk and Suffolk NHS Foundation Trust embedding cultural awareness within service evaluation and PCREF implementation?
A question was raised regarding how patient and carer feedback is systematically captured, and whether cultural awareness is meaningfully integrated into trust surveys, service audits, and PCREF rollouts rather than treated as a tick-box exercise.
Response:
Cath Byford acknowledged that standard feedback mechanisms often fail to capture the nuanced experiences of minoritised communities. She explained that the trust is refining its data collection tools alongside its Health Equity team and local carers to ensure feedback loops directly inform clinical practice and PCREF operational plans.
Q2. How are intersectional barriers such as neurodivergence and criminal justice involvement being addressed for minoritised families?
A detailed discussion focused on the severe intersectional challenges faced by minoritised families, particularly where mental health conditions overlap with neurodivergence or involvement in the criminal justice system. Concerns were raised that carers face immense financial and logistical hurdles to attend meetings or advocate for relatives.
Response:
Cath and Annie agreed that intersectionality must be at the forefront of service design. The panel emphasized that research teams and trust steering groups must formally budget for carer access needs—including funding for sitters, respite, and transport—to enable equitable participation from grassroot carers.
Q3. How can NHS trusts move away from generic terminology like “BAME” to build trust with specific communities?
Contributors stressed the importance of discarding outdated, homogenized labels such as “BAME” in favor of recognizing specific ethnic and cultural identities. Members questioned how trusts plan to engage directly with local grassroot organizations rather than relying on top-down communications.
Response:
The presenters affirmed that language matters deeply in establishing trust. NSFT is focusing on direct partnerships with Voluntary, Community, and Social Enterprise (VCSE) sector organizations that already hold trusted relationships within specific cultural communities, ensuring engagement is authentic and localized.
Keynote Address: Competence, Leadership, and Race Equity
Speaker: Lord Victor Adebowale (Chair, NHS Confederation & Founder, NHS Race and Health Observatory)
Lord Victor Adebowale delivered a sweeping keynote address that fundamentally challenged traditional healthcare perspectives on race equity, anti-racism, and organizational accountability. Moving the discussion away from performative pledges and symbolic gestures, Lord Victor framed racial equity not as an optional moral, social, or political stance, but as a core requirement of clinical and operational competence.
He began by reframing the definition of leadership within the healthcare ecosystem, asserting that unpaid family carers act as leaders every single day. Through their daily advocacy, continuous care coordination, and tireless protection of vulnerable family members, carers demonstrate true leadership long before health systems officially acknowledge their presence.
Lord Victor drew stark attention to the persistent impact of the Inverse Care Law, illustrating how individuals from the global majority routinely receive poorer quality services and face worse health outcomes despite presenting with the highest levels of clinical need. He warned that system-wide failure to serve minoritised families cannot be viewed as an isolated issue; when a healthcare trust tolerates substandard, culturally unsafe care for Black and ethnic minority service users, the overall quality, safety, and effectiveness of care inevitably degrades for every patient using that service.
A central theme of his address focused on moving the national conversation away from an endless reliance on individual conscious or unconscious bias training. Lord Victor argued that over-emphasizing implicit bias often allows healthcare systems to evade operational accountability. Instead, anti-racism must be treated as a strict benchmark of professional capability. Leaders and clinicians who fail to deliver equitable care across diverse populations are not simply displaying personal bias they are actively choosing to operate incompetently. He insisted that health trust boards must begin holding executive leadership to the exact same rigorous accountability standards for race equity as they do for clinical safety and financial management.
Furthermore, Lord Victor emphasized that unpaid family carers represent the primary early-warning system within the entire healthcare structure. Carers are routinely the first to spot subtle signs of deterioration or service failure, often weeks before clinical teams become aware of an emerging crisis. He condemned the institutional practice of dismissing carer insights under the blanket rationale of “patient confidentiality,” warning that using information governance as an excuse to shut out family members discards the most valuable clinical intelligence available and actively compromises patient safety.
Four Rules for Authentic Community Engagement
To guide health trusts and Integrated Care Boards (ICBs) toward genuine structural reform, Lord Victor outlined four non-negotiable rules of engagement when working alongside minoritised communities and family carers:
Listen with Evidence of Being Heard: Listening exercises and consultation events are entirely meaningless unless community members and carers are provided with clear, practical evidence showing exactly how their feedback altered decisions, policies, or service delivery.
Transfer Real Power: Authentic engagement requires a fundamental shift in traditional power dynamics. Healthcare institutions must share authority and transfer tangible resources so that minoritised communities are empowered to act independently and lead changes themselves.
Equal Partnership over Superficial Co-production: Health systems must move beyond tokenistic co-production exercises, which often amount to seeking quick feedback on pre-written plans—and commit to long-term, equal governance partnerships where carers sit at the decision-making table from inception to evaluation.
Describable and Transparent Outcomes: Any service alteration or policy development resulting from community engagement must produce clear, tangible outcomes that are easily understood, described, and validated by the community itself, rather than hidden behind dense NHS jargon.
Matthew’s Question
Matthew raised concerns regarding the persistent barriers unpaid carers face—specifically questioning how health systems can stop excluding ethnic minority carers through medical jargon and information gatekeeping (such as using “confidentiality” as an excuse to exclude families), and how trusts can be held genuinely accountable under frameworks like the Patient and Carer Race Equality Framework (PCREF).
Lord Victor Adebowale’s Response
Lord Victor addressed this by framing race equity and carer involvement as a matter of operational and clinical competence rather than optional policy:
Reframing Carer Insights: He emphasized that family carers are the primary early-warning system in healthcare who spot signs of deterioration weeks before clinical teams. Dismissing carer insights using “confidentiality” throws away vital clinical data and actively compromises patient safety.
Competence over Bias: He stated that leaders who fail to provide equitable care to minoritised families or exclude carers are choosing to operate incompetently. Boards must hold executive leadership accountable for race equity to the exact same standards as clinical safety and financial management.
Rules of Engagement: He outlined that genuine engagement requires health trusts to listen with evidence of being heard, transfer real power to communities, build equal partnerships, and deliver transparent, describable outcomes that the community can easily see and verify.
Questions and Discussion
Q1. Why are Black men in mental health services disproportionately subjected to high doses of medication rather than holistic therapies?
A critical question was raised regarding why Black men entering acute mental health pathways are frequently managed through high-dose psychiatric medications and prolonged admissions rather than being offered timely talking therapies, early intervention, and holistic community support.
Response:
Lord Victor emphasized that over-reliance on medication and restrictive practices reflects systemic clinical failure and risk-averse institutional cultures. He stressed that true clinical competence requires services to offer culturally appropriate psychological interventions and preventative care early in the care pathway, rather than defaulting to chemical containment during crises.
Q2. How can healthcare systems better support the emotional, financial, and legal well-being of long-term family carers?
A forum contributor shared their personal experience as a sole carer managing a mother with vascular dementia and Alzheimer’s in rural Gloucestershire. They highlighted the severe isolation, legal hurdles, and financial exhaustion experienced by carers, asking directly: “Who is caring for the carer?”
Response:
Lord Victor and forum members acknowledged the systemic neglect of carer well-being. The discussion highlighted that supporting carers is a clinical necessity, not an optional luxury. Practical signposting was shared, pointing members toward specialist support networks and helplines, including Dementia UK, while calling on Integrated Care Boards (ICBs) to fund dedicated carer respite initiatives.
Research Updates: Amplifying Carer Voices
1. Black Carers and Learning Disability Services
Presenter: Lorraine Heath (Trainee Clinical Psychologist, University of Southampton)
Lorraine Heath introduced her doctoral research project exploring the complex, intersectional barriers that Black family carers encounter when navigating mental health and learning disability services on behalf of their relatives. Lorraine explained that while national policy increasingly highlights health equity, Black families caring for loved ones with learning disabilities continue to face profound structural, institutional, and cultural hurdles. These challenges frequently result in delayed access to vital support, misdiagnosis, or total exclusion from essential statutory services.
The research focuses on capturing the lived realities of Black carers across both child and adult services including Child and Adolescent Mental Health Services (CAMHS) and adult community mental health teams to understand how healthcare systems can better support families before crisis points occur. Lorraine emphasized that unpaid Black carers often have to act as fierce advocates, interpreters of complex care systems, and primary safety nets, often without receiving adequate recognition or formal support from service providers.
Research Objectives: The study aims to map out the specific diagnostic pathways, institutional barriers, and negative experiences that Black families face when seeking care. By identifying where services fail to provide culturally sensitive, timely support, the project seeks to build a robust evidence base to influence future clinical practice, service design, and commissioning standards across NHS mental health and learning disability teams.
Methodology & Care for Participants: Recognizing that discussing institutional barriers and negative service interactions can be emotionally draining, the study utilizes 90-minute flexible online interviews via Microsoft Teams, designed around the participant’s schedule and comfort. To ensure lived experience is meaningfully valued rather than exploited, all participants receive a £25 shopping voucher as a token of appreciation for their time and contribution. Furthermore, strict data protection protocols are embedded throughout the study to guarantee complete anonymity for all participating carers.
Lorraine invited members of the forum to share details of the study within their local networks, encouraging Black family carers with relevant lived experience to participate and ensure their voices shape future mental health provision.
Questions and Discussion
Q1. How will the study protect Black carers from re-traumatisation when discussing negative service experiences?
Forum members inquired about the safeguarding protocols in place for participants who may experience distress while recalling challenging interactions with health and social care services.
Response:
Lorraine confirmed that emotional safety is central to the study design. Pre-interview briefings, built-in debriefing sessions, and immediate signposting to culturally sensitive psychological support are provided to all participants.
2. Supporting the Supporters: Integrating Informal Carers
Presenter: Carol Garbutt (King’s College London)
Carol Garbutt introduced her master’s research project, Supporting the Supporters, which addresses the critical breakdown in communication and partnership between professional healthcare services and informal family carers. Carol explained that despite longstanding national directives highlighting the importance of involving family members, unpaid carers from minoritised backgrounds are routinely sidelined, excluded from decision-making, or left without basic support when supporting a relative through the mental health system.
The study explores the organizational culture, professional attitudes, and systemic practices that dictate how informal carers are treated across clinical settings. Carol highlighted that while professional staff often view safety and treatment solely through the lens of individual patient care, unpaid carers are the ones managing day-to-day crises, monitoring medication side effects, and providing essential emotional and practical stabilization at home. Failing to integrate these informal support networks into formal care planning not only places an overwhelming burden on family members, but actively compromises patient safety and recovery.
Research Scope & Focus: The study focuses on gathering perspectives from across the mental health ecosystem including professional healthcare workers, clinical staff, patient advocates, and voluntary sector leaders. By examining how professionals define, view, and interact with family carers, the research aims to pinpoint the precise organizational obstacles and misalignments that lead to carer exclusion.
Project Goals & Impact: The overarching objective is to build a robust, practice-informed evidence base that pushes mental health trusts to embed family carers into standard clinical workflows. Carol emphasized that true integration requires moving beyond informal signposting toward establishing clear communication protocols, ensuring carers are formally identified at the point of admission, and treating them as equal, valued partners in care planning and discharge processes.
Questions and Discussion
Q1. How does the research address instances where professionals hide behind confidentiality rules to exclude carers?
Members highlighted that staff frequently cite information governance to withhold basic care updates from family members.
Response:
Carol explained that her study specifically examines professional attitudes and organizational policies surrounding communication. The goal is to highlight best-practice frameworks that allow clinicians to share essential care planning details with families while respecting patient rights.
3. Partners’ Experiences of Gynaecological Cancer
Presenter: Lara (Trainee Clinical Psychologist, University of Hertfordshire)
Lara introduced her doctoral research exploring the lived experiences of partners supporting individuals diagnosed with gynaecological cancer.
Research Focus: Examining the complex emotional, physical, relational, and financial impacts on partners navigating a gynaecological cancer diagnosis.
Project Goal: Tackling cultural taboos and stigma surrounding gynaecological health, providing evidence to help cancer charities and NHS trusts design tailored psychological and practical support packages for partners.
Questions and Discussion
Q1. How does the study account for cultural stigmas surrounding gynaecological health within minoritised communities?
Carers noted that discussion of gynaecological health remains heavily stigmatized in many ethnic communities, which can prevent partners from seeking external help.
Response:
Lara acknowledged these cultural complexities, explaining that the interview frameworks are designed to be sensitive to diverse cultural norms, allowing participants to share their experiences in a safe, non-judgmental environment.
Creative Advocacy: Combatting Gatekeeping Through Poetry
Matthew McKenzie presented a video poem developed as part of his ongoing advocacy work surrounding the Patient and Carer Race Equality Framework (PCREF).
Using creative media and spoken word, the poem visually and emotionally illustrates the everyday barriers faced by ethnic minority carers including institutional gatekeeping, dense medical jargon, exclusion from multi-disciplinary team meetings, and the sensation of being rendered invisible by healthcare professionals.
Matthew emphasized that creative media and arts-based advocacy are powerful mechanisms for staff training. By translating complex policy frameworks like PCREF into lived emotional narratives, creative media helps NHS staff understand the human impact of structural exclusion and drives empathetic, anti-racist practice across clinical teams.
Key Takeaways and Next Steps
The August meeting highlighted several critical action points for the forum and its partner organizations:
Accountability over Intent: Moving beyond policies, anti-racism charters, and pledges to demand measurable, transparent outcomes in patient care and carer satisfaction.
Dismantling Institutional Gatekeeping: Working with NHS trusts to ensure family carers are identified and involved early in treatment pathways, dismantling the misuse of confidentiality as a barrier.
Embedding Co-Production: Supporting minoritised carers to join trust boards, steering groups, and PCREF advisory panels to ensure lived experience directly shapes local health delivery.
Looking Ahead to September:
The next national forum meeting will feature updates from Sheffield Health and Social Care NHS Foundation Trust, the Race Equality Foundation, Black Country Healthcare NHS Foundation Trust, and regional carer networks.
By Matthew McKenzie, Co-Facilitator – South West London Mental Health Carers Forum
The South West London Mental Health Carers Forum met again during August 2026, bringing together unpaid carers to share experiences, discuss how the forum is developing and look at ways we can strengthen the voice of carers across South West London.
The forum continues to be a peer-led space shaped by carers themselves. An important message from the August meeting was that this is a group for carers, run with carers and influenced by carers. Members spoke about wanting people who join the forum to feel recognised, valued and able to support one another, rather than the group becoming overly formal or service-led.
By Matthew McKenzie – Facilitator of Cancer Caregiver group
It has been a long while since I published a full update from my National Cancer Caregiver Forum. Although I have continued working to raise awareness of unpaid cancer caregiving, this latest meeting reminded me why the forum remains so necessary.
The National Cancer Caregiver Forum provides an online space for people caring for someone affected by cancer, former carers, researchers and organisations interested in improving support. It combines peer support with engagement, research and opportunities to influence cancer services.
Why cancer caregivers still need a voice
I opened the forum by reflecting on the shortage of dedicated groups for unpaid cancer carers. There are many services and support groups for people receiving cancer treatment, as there should be, but far fewer spaces focused specifically on the partners, relatives and friends supporting them.
On Monday 24 August, I facilitated another meeting of the South London Mental Health Carers Forum. The forum brings together unpaid carers and carer representatives from Lewisham, Lambeth, Southwark and Croydon, giving people a space to share experiences, learn about their rights and influence the development of local mental health services.
We welcomed carers with many different experiences, including parents supporting adult children with serious mental illness, autism and substance misuse, as well as people involved in advocacy, peer support, staff training and service development. Some members had been navigating the mental health system for many years, while others were newer to caring and looking for guidance.
A powerful message emerged from the introductions: even experienced carers can struggle to understand how different parts of the mental health system fit together. Services can feel fragmented, with carers passed between teams or excluded from discussions despite holding important information about their loved one’s history, warning signs and support needs.
Supporting the Supporters research
We were joined by Carol, an unpaid carer and postgraduate student studying psychology and neuroscience of mental health at King’s College London.
Carol introduced her research project, Supporting the Supporters: Professional Perspectives on Integrating Informal Care into the Mental Health Ecosystem. The study explores how professionals understand the contribution made by unpaid carers, how information and support could be improved, and how carers could be more meaningfully involved alongside mental health professionals.
As part of the research, Carol is interviewing people with professional or advocacy perspectives, including psychologists, psychiatrists, GPs, commissioners, teachers, service providers and carer advocates. I have already taken part in an interview, and several forum members expressed an interest in contributing.
The discussion highlighted why it is so important for carers’ experiences to be represented in academic research. Research can help shape future policy and practice, but carers also stressed that participants should be kept informed about what happens to the findings. Too often, people share deeply personal experiences with research projects and never hear about the outcome.
I also informed members about a separate University of Oxford study exploring wellbeing and social-group attendance among people caring for someone with a serious mental illness. We hope to hear more about this opportunity at a future meeting.
Triangle of Care: more than an accreditation badge
The main presentation focused on the Triangle of Care, a framework developed by Carers Trust to improve cooperation between the person receiving mental health services, the professionals supporting them and their unpaid carer.
As facilitator, I explained that the framework should be something carers experience in practice, not simply an accreditation badge displayed by an organisation.
South London and Maudsley NHS Foundation Trust has achieved Triangle of Care Star 1 for inpatient services and Star 2 for community services. With this work now being reviewed, there is an important opportunity for carers to help examine whether the standards are making a noticeable difference across local services.
Carers should be recognised and recorded, listened to when they provide relevant information, given clear explanations about confidentiality, offered appropriate information and support, and involved at important points in care and discharge planning. Staff should also understand that carers have needs and rights of their own.
Confidentiality should not become exclusion
Confidentiality produced one of the most detailed and passionate discussions of the meeting. Several carers described situations in which confidentiality had been used to shut down communication completely.
Respecting the service user’s privacy is essential, but confidentiality does not prevent professionals from listening to a carer’s concerns. A carer may hold vital information about changes in behaviour, medication, relapse indicators, risks or what the person is like when well.
Even when professionals cannot disclose personal clinical information, they can usually provide general information about how a service works, explain how a carer can submit concerns and signpost the carer towards available support. Carers should not simply be told, “We cannot speak to you,” and then left without guidance.
Members also discussed situations where a person experiencing a serious deterioration may withdraw consent for family involvement. These cases require careful professional judgement, particularly where there may be questions about safety, insight or decision-making ability. Carers felt that staff need more confidence and training to manage these situations without automatically treating the family as a problem.
Carers were encouraged to ask whether their role has been recorded, how they can share information with the clinical team, how they will be involved in care and discharge planning, and who they can approach if their perspective is being overlooked. Where serious concerns are ignored, carers should raise them in writing so there is a clear record.
Carer involvement in discharge
The discussion then moved to hospital discharge. Carers can sometimes be contacted shortly before someone returns home, without a proper conversation about whether they are able or prepared to provide the expected support.
A safer discharge should include an early discussion with the carer about the help they can realistically offer. Information about medication, warning signs, follow-up arrangements and points of contact should be explained clearly. Professionals should not assume that a family member can take on intensive caring responsibilities simply because they are related to the person.
Carers also need to know that they can request a carer’s assessment from their local authority. An assessment can help identify the effect caring is having on their own wellbeing and what support may be needed. Existing assessments should be reviewed when circumstances or caring responsibilities change.
What carers raised during the forum
A substantial part of the meeting was led by carers sharing what they had experienced while supporting relatives through mental health services. Although everyone’s circumstances were different, many common concerns emerged across Lewisham, Lambeth, Southwark and Croydon.
Several carers described the mental health system as fragmented and difficult to navigate. Families may deal with inpatient wards, community mental health teams, crisis services, supported accommodation, GPs and social care, but these services do not always appear to communicate effectively with one another. One carer reflected that even after years of involvement, it can still be difficult to know whom to contact when a new crisis develops. This raised concerns about how much harder the system must be for people who are new to caring.
Carers also felt that decisions made at senior levels do not always reflect what happens in practice. Policies, pathways and strategies may appear clear on paper, but families can experience delays, poor communication and a lack of coordination. Members wanted more people with direct experience of using or working within mental health services to influence decisions at the highest levels.
A major concern was the failure to listen when carers report early signs of deterioration. Carers often recognise changes in sleep, behaviour, medication use, substance misuse or communication long before a situation reaches crisis point. Some members described situations in which their warnings were overlooked, only for the person’s condition to worsen later. Carers felt that their observations should be recorded and considered as part of risk assessment and relapse prevention, even when professionals cannot share confidential clinical information in return.
Confidentiality was one of the most strongly debated issues. Carers understood that people using mental health services have a right to privacy. However, they felt that confidentiality is sometimes interpreted too rigidly and used to exclude families from almost every conversation.
The group stressed that professionals can still listen to information provided by a carer. They can also explain how the service operates, receive concerns, provide general guidance and direct the carer towards support. Saying “we cannot tell you anything” should not bring all communication to an end.
Some carers described being excluded after their relative had withdrawn consent for family involvement, sometimes during a period of serious illness or limited insight. Members questioned how consent is considered when someone’s mental state or decision-making ability may be changing. They felt staff should look carefully at the individual circumstances, risks and history instead of applying confidentiality as an automatic barrier.
The inconsistency between professionals was another concern. Some staff members communicate sensitively and recognise the value of family knowledge, while others refuse even to listen. Carers felt that the quality of their involvement should not depend on which professional happens to answer the telephone. Better training, management support and accountability are needed so that good carer practice becomes consistent across services.
There was also discussion about inaccurate or outdated information remaining in health records. Carers described how an early diagnosis, allegation or misunderstanding can continue to influence future treatment long after it has been challenged. Correcting such information can be extremely difficult, yet it may affect how professionals view both the person receiving care and their family. Members wanted clearer ways to challenge inaccuracies and ensure that corrections or alternative professional opinions are properly recorded.
Carers raised concerns about attitudes towards families. While relationships can sometimes be complicated, relatives should not automatically be viewed as interfering or obstructive. Where disagreements arise, members suggested that an independent person, advocate or senior professional could help everyone understand the different perspectives. Completely blocking communication can damage family relationships and may also undermine the person’s recovery and safety.
The experiences of carers from racialised communities were also recognised. One member spoke about the fear and mistrust that can develop when Black men repeatedly come into contact with mental health services or the criminal justice system. The forum acknowledged the importance of culturally responsive services that understand how race, stigma, previous experiences and unequal treatment can affect whether families feel safe seeking help.
Hospital discharge was another prominent concern. Some carers reported being contacted too late, with an expectation that they would immediately resume significant caring responsibilities. Members felt carers should be involved early enough to discuss what support they can realistically and safely provide. They should receive clear information about medication, warning signs, follow-up arrangements and who to contact if the person’s condition deteriorates.
Carers should not be treated as an unlimited resource. Being a parent, partner, sibling or other relative does not automatically mean someone is physically, emotionally or practically able to provide the level of support being assumed. The carer’s own health, employment, family responsibilities and wellbeing must be considered during care and discharge planning.
Members also discussed the importance of carer’s assessments. Some people had received very few assessments despite caring for many years. Carers were encouraged to request an assessment from their local authority and to seek a review when their responsibilities or personal circumstances change. An assessment creates a formal record of the caring situation and may identify support needed to protect the carer’s wellbeing.
Another recurring issue was accountability. Guidance about involving carers may exist, but families are not always sure what to do when services fail to follow it. Members were encouraged to put important concerns in writing, keep records of correspondence and ask for matters to be escalated when necessary. A clear written record can become particularly important if warnings have been ignored or a serious incident later occurs.
Despite these difficult experiences, the conversation also demonstrated the strength of peer support. Carers shared knowledge, validated one another’s concerns and helped newer members understand that they were not alone. The group strongly encouraged carers not to remain isolated, even when their loved one appears relatively well. Joining a carers’ centre, peer-support group or advocacy forum can provide information and connections before another crisis occurs.
The overall message from carers was clear: they are not asking to take over clinical decisions. They are asking to be recognised as people with valuable knowledge, their own support needs and an important role in safer care. The Triangle of Care will only have meaning if carers can see and feel these principles operating in their everyday contact with services.
Turning shared experience into influence
This meeting demonstrated why independent, carer-led forums remain so important. They reduce isolation, allow newer carers to learn from those with longer experience and help identify patterns that may otherwise be dismissed as individual incidents.
Members involved in SLaM meetings and the forthcoming carers’ listening event were encouraged to raise the Triangle of Care and ask how carers will contribute to its review. I will also seek to invite representatives leading this work at SLaM to a future forum so that they can update carers directly and respond to questions.
Our next South London Mental Health Carers Forum is due to take place on Monday 28 September 2026. We will continue examining the Triangle of Care, with a stronger focus on carers’ experiences and the practical changes they want to see across mental health services.
I would like to thank everyone who attended and spoke so openly. The experiences shared were sometimes difficult, but they reinforced an important principle: carers should not have to fight simply to be recognised, heard and supported.
My latest poetry video, “Gatekeeping Care,” explores the barriers minority ethnic unpaid carers can face when trying to navigate mental health services.
This is where unwritten rules, complicated medical language and unexplained carer rights can leave people struggling to understand how to obtain support.
Unpaid carers can also have their concerns not taken seriously.
The poem also reflects on what it feels like when decisions are made without carers and their cultural or religious beliefs are overlooked.
Through this poem, I want to raise awareness of why the Patient and Carer Race Equality Framework (PCREF) matters to carers and families.
I feel mental health services must listen to carers, communicate clearly and recognise them as equal partners rather than leaving them feeling judged, invisible or powerless.