By Matthew McKenzie – Chair of the Greenwich Mental Health Carers Forum
Welcome to the September update of the Greenwich Mental Health Carers Forum, held on Tuesday 29 September 2026.
This month, we welcomed representatives from Greenwich Carers Centre, the Royal Borough of Greenwich, Healthwatch Greenwich and Greenwich Mental Health Hub, alongside unpaid carers.
Our discussion explored the future of carer support in Greenwich, difficulties accessing respite, support available through the Mental Health Hub, and how carers’ feedback can influence services.
For those unable to attend, here is an overview of the meeting.
Greenwich Carers Centre: opportunities to connect and receive support
Catherine Hope joined us on behalf of Greenwich Carers Centre to share its forthcoming activities.
The programme included employment and digital support, the Mindcare Memory Café, a men’s carers group, karaoke, bereavement support, and information sessions about wills and disabled persons’ trusts. A community health event was also highlighted for late October.
Alongside these events, the Centre continues to offer regular activities such as dance, art, Tai Chi, knitting and social gatherings.
These opportunities matter because caring can leave little time for friendship, enjoyment or attention to our own wellbeing. A welcoming place to meet others can make a considerable difference.
Carers interested in attending should contact Greenwich Carers Centre for the latest programme, booking arrangements and eligibility information.
Shaping the future of carer support in Greenwich
Caleb and Evie from the Royal Borough of Greenwich commissioning team updated us on work to review commissioned carer services and prepare for the next stage of the borough’s carers strategy.
The current strategy comes to an end in 2027. Commissioners have been gathering feedback through workshops, carers groups and community engagement, including sessions focused on mental health carers and culturally inclusive support.
They explained that this feedback is helping shape the requirements for future carer services. It will also inform thinking about a future strategy or charter, although the final approach has not yet been decided.
The intention is to develop proposals and return to carers groups, potentially early next year, to check whether those proposals reflect what carers have said.
I welcome that commitment to return. Carers need opportunities to see how their experiences have influenced decisions and to challenge proposals where something important has been missed.
Respite: carers need breaks that work in everyday life
Respite was one of the strongest themes raised during the meeting and across the council’s wider engagement.
Commissioners reported concerns about access, suitability, affordability and the complexity of finding the right support.
Our discussion showed why respite needs to fit the realities of caring. Some carers need a longer break, while others need smaller, regular periods of rest within their weekly routine.
One carer described difficulties obtaining support when the person they care for lives in accommodation in another borough. Their caring responsibilities continue despite living at different addresses.
This raised an important issue: services need to understand the care someone actually provides, including practical support, emotional support and ongoing responsibility across borough boundaries.
Commissioners also described an apparent mismatch between carers reporting a strong need for breaks and some commissioned respite beds remaining unused. They are exploring why this is happening and where access arrangements may be failing.
For me, this is a clear example of why listening to carers matters. The existence of a service does not tell us whether people can use it or whether it meets their needs.
How does feedback reach people who can change services?
I asked how concerns about difficult-to-access or unsuitable services reach those responsible for making improvements.
The commissioning team explained that they have brought together feedback on respite into a report and are sharing it with colleagues responsible for different services, including learning disability, mental health and care home provision.
Other concerns, including carers’ assessments, direct payments and support for parent carers, require work across several teams.
They acknowledged that the timescale for change varies. Some improvements may be possible through changes to contracts, while others require longer-term planning.
The team also expressed an interest in publishing an account of what they have heard and what they intend to do.
That would be a useful step towards accountability. Carers should be able to follow the connection between the experiences they share, the decisions made and the improvements delivered.
Earlier identification and culturally inclusive support
Commissioners highlighted several recurring themes from their engagement:
Inconsistent information and advice across services.
Missed opportunities to identify carers earlier.
Difficulty navigating health and social care.
A need for more proactive support.
The importance of trust and relationships.
Barriers involving access to interpreters.
The discussion about interpreting was particularly important. Carers should be able to explain their situation, understand information and take part in decisions in a language they can use confidently.
The council’s culturally inclusive engagement has also explored systemic barriers and anti-racist approaches to commissioning.
There was positive feedback too. Commissioners reported that carers place a high value on peer support, with Greenwich Carers Centre described by some as a lifeline.
Greenwich Mental Health Hub: understanding the support available
Jackie, representing Greenwich Mental Health Hub, gave a detailed presentation about its integrated approach.
The Hub brings together Oxleas clinical services and voluntary sector partners, including South East London Mind and Bridge Support. Its aim is to offer personalised support that considers someone’s psychological, physical and social circumstances.
The presentation described support involving:
Mental health assessment and brief interventions.
Medication advice and support.
Peer support and group programmes.
Housing, benefits and employment advice.
Social prescribing and community connections.
Support with co-occurring mental health and alcohol difficulties.
A dedicated carers advisor.
Jackie explained that much of the Hub’s work involves short-term support, generally around 12 weeks, with onward referral where further help is needed.
She also reported more than 7,000 referrals over the preceding year, illustrating the scale of demand.
Referral routes and carers’ concerns about deterioration
I asked what happens when a carer notices that the person they support is becoming more unwell, and how that information reaches the appropriate team.
In the discussion, Jackie described the GP referral route into the Hub. She explained that carers seeking their own support would also generally need a GP referral unless they were already receiving support through an active Hub referral.
The Hub was described as an appointment-based service rather than a walk-in service.
Jackie explained that referrals are screened regularly and urgent referrals prioritised. Screening is an initial review of the referral; it should not be confused with a confirmed appointment or treatment starting immediately.
These questions remain important for carers. When someone’s health is deteriorating, families need clear information about who to contact, how concerns are considered and what happens next.
Carers’ assessments and waiting for support
A carer raised concerns about waiting for a carers’ assessment without being given a clear timescale.
The discussion clarified that a local authority carers’ assessment and a mental health assessment through the Hub serve different purposes. One looks at the caring role and its impact; the other considers mental health support needs.
The carer was encouraged to ask the council for an expected timescale. An offer was also made to seek information about average waiting times and follow up.
The forum did not establish a confirmed waiting period. However, the discussion highlighted how uncertainty itself adds pressure when someone is already struggling.
Community organisations and mental health inequalities
Jackie also described the Hub’s grants programme supporting community organisations to provide mental health support.
She reported that ten community groups had received funding over the past year. The approach recognises that trusted local organisations can help people access support, particularly where stigma or other barriers make conventional services difficult to approach.
Further information about the grants was requested during the meeting.
Healthwatch Greenwich: another route for sharing experiences
Katie from Healthwatch Greenwich explained how residents can share experiences of health and social care, including through conversations and anonymous online feedback.
She described how information is anonymised when reported to commissioners, helping services understand what is working and where improvements are needed.
For carers who would prefer to speak privately rather than share an experience in a group, this offers another route to contribute.
Looking ahead
Thank you to all the carers and professionals who joined the September forum.
The meeting showed both the value of existing support and the difficulties carers still face. Respite, clear referral routes, timely assessments, consistent information and earlier recognition of caring responsibilities all need continued attention.
Our next Greenwich Mental Health Carers Forum is planned for November. I look forward to continuing these discussions and hearing how the feedback shared by carers is being taken forward.
As I continue developing my poetry collection Unpaid, Unseen and Yet Unbroken: Poetry about Ethnic Mental Health Carers, I wanted to share another poem from the collection called Fear Has Roots.
The poem explores something I feel mental health services need to understand more deeply: mistrust does not always begin with the person standing in front of you.
Sometimes it has a history.
A carer may have experienced years of being dismissed, misunderstood or having their concerns minimised. They may have watched other carers from their community struggle to be heard. Experiences of discrimination can also travel through families and communities, influencing how safe people feel when approaching services.
Fear Has Roots explores what happens when those experiences begin to change the way a carer communicates.
The carer starts choosing their words carefully. They worry about appearing angry. They fear being labelled “difficult” or “aggressive”. Even when trying to advocate for someone they love, they may feel that one wrong word could change how professionals see them.
One section of the poem says:
For me, this is particularly important when thinking about ethnic minority carers and the Patient and Carer Race Equality Framework (PCREF).
If services want to build trust with communities, it is not enough simply to ask why somebody mistrusts the system. We also need to ask what happened before that mistrust developed.
Listening to what sits behind the fear
The poem is not anti-professional. In fact, its opening line deliberately makes that clear:
“Fear has roots, I am not anti-professional.”
Instead, it asks professionals and services to become curious about the experiences behind a carer’s behaviour.
Repeated dismissal can wear somebody down. Discrimination can leave lasting memories. Feeling judged when advocating for a loved one can make a carer more cautious the next time they enter a meeting, ward or assessment.
This is why culturally responsive carer involvement matters.
We should not only hear what carers are saying. We should also understand the history, culture and experiences that may sit behind their words.
Fear has roots.
Mistrust has a history.
And perhaps listening is one of the places where rebuilding trust can begin.
Fear Has Roots is part of my developing poetry collection Unpaid, Unseen and Yet Unbroken, which explores race, culture, identity, inequality, resilience and the experiences of ethnic minority unpaid mental health carers.
Think Tenacity Academy CIC is hosting another important Making Time for Black Mental Health event in London.
The free racial trauma seminar will take place on:
Wednesday 23 September 2026 3:00 pm–9:00 pm Cottons Shoreditch, 321 Old Street, London EC1V 9LE
The event will provide a culturally informed space to explore racial trauma, mental health and wellbeing within Black communities. It will also create opportunities for people with lived experience, carers, professionals and community organisations to connect and learn from one another.
I attended a previous Making Time for Black Mental Health event and saw how valuable these community-led spaces can be. They enable conversations about race and mental health to take place in an environment where people feel understood, represented and supported.
As a lived experience Black mental health carer and advocate, I know that racial trauma can affect not only individuals but also families and unpaid carers. We need more culturally responsive spaces that recognise these experiences and make it easier to discuss mental health without fear, judgement or stigma.
The event is free to attend, but capacity is limited to approximately 45 places, so early booking is strongly recommended.
A related Racial Trauma Group Support event is also advertised for Thursday 1 October in Notting Hill.
By Matthew McKenzie – Chair of ethnic MH Carer forum / Chair of Cancer Carergiver group
I was recently sent information about an important cancer care project being led by Learning Disability England in partnership with the Race Equality Foundation which is funded by Macmillan Cancer Support.
The project aims to improve cancer care for people with learning disabilities from Black, Asian and minoritised ethnic communities. A working group is being established involving self-advocates, family members and friends who have experience of cancer.
Healthwatch Lambeth is inviting patients and unpaid carers to share their experiences of leaving hospital.
The survey is part of a nationwide Healthwatch England project examining hospital discharge. Healthwatch Lambeth is particularly seeking responses from people living in Lambeth who have experienced a difficult hospital discharge within the past 12 months.
This may include situations where:
Discharge was delayed.
The patient was sent home before they felt ready.
Information about the discharge was unclear or incomplete.
Essential equipment or support was not available.
Follow-up care had not been properly arranged.
An unpaid carer was not sufficiently involved, informed or prepared.
The survey can be completed by patients themselves or by an unpaid carer describing the experience of someone they care for.
Healthwatch Lambeth is especially interested in hearing from people whose experiences may not always be represented in health and care feedback, including men and people from ethnic minority communities.
Hospital discharge can place significant responsibility on families and unpaid carers. When carers are not recognised, involved or given the right information, they may suddenly find themselves managing medication, personal care, appointments and recovery without adequate preparation.
Sharing these experiences can help identify what needs to improve and highlight the importance of involving carers as genuine partners throughout discharge planning.
Please share this survey with Lambeth residents, patients and unpaid carers who may have had a difficult hospital discharge experience during the past year.
Black unpaid carers can face significant barriers when trying to access mental health support for themselves or the person they care for.
These difficulties may include long waiting times, financial pressure, cultural stigma, fear of statutory services and a shortage of professionals who understand the effects of racism, racial trauma and culturally specific caring experiences.
In my new video, I examine how misdiagnosis, over-policing and expectations that Black families should simply remain “strong” can create mistrust and discourage carers from asking for help.
Drawing on my perspective as a Black lived-experience carer, I also consider what mental health services can do differently. Genuine improvement requires culturally responsive support, greater representation, safe spaces for carers, accessible community-led services and meaningful partnership with Black carers and families.
PCREF provides an important opportunity to challenge racial inequalities, but its success will depend on whether services listen to lived experience and turn commitments into visible action.
By Matthew McKenzie – Chair, National Ethnic Mental Health Carers Forum
The July meeting welcomed unpaid carers, NHS organisations, universities, researchers and community groups from across England to discuss how mental health services can become more inclusive for carers from ethnic communities.
Matthew McKenzie opened the meeting by reflecting on over thirteen years of facilitating the forum and explained how its purpose has grown alongside national initiatives such as the Patient and Carer Race Equality Framework (PCREF) and the Triangle of Care. The forum continues to provide a national platform where carers can influence NHS services, hear about new research and share experiences with professionals and decision-makers.
Matthew introduced the day’s programme, which included research presentations, NHS England engagement, updates from mental health trusts and national organisations, and opportunities for carers to influence future policy
Dr Ida Doherty – King’s College London
Supporting Ethnic Carers in South West London
Dr Ida Doherty presented her doctoral research exploring how adult mental health services support ethnic minority families where a parent experiences mental illness.
She explained that despite national policy promoting a Think Family approach, implementation across England remains inconsistent. Many parents receiving mental health support are never asked about their children, meaning opportunities for preventative family support are often missed.
Discussion Highlights
This presentation generated one of the longest discussions of the meeting.
Carers highlighted:
Adult and children’s services continue to work separately.
Families often have to repeat their stories to multiple organisations.
Parents fear seeking support because of concerns about children being removed.
Structural racism continues to affect safeguarding and mental health services.
Disabled parents and carers experience multiple layers of discrimination.
Services often respond only during crisis rather than providing early intervention.
There was also an important discussion about safeguarding carers who participate in research. Participants stressed that research should include emotional support, culturally appropriate safeguarding and co-produced approaches to prevent re-traumatisation. Dr Doherty welcomed these suggestions and explained the safeguarding measures built into her study.
Dr Doherty encouraged forum members to promote the study across South West London to help ensure ethnic families are represented within the research.
Certainly. Here’s a more professional version that focuses on the discussion rather than identifying who asked each question.
Questions and Discussion
Q1. How can mental health services better implement the “Think Family” approach?
A question was raised about the continuing separation between children’s and adult mental health services, with concern that families are often required to navigate multiple systems that fail to communicate with one another. It was suggested that supporting one family member in isolation overlooks the wider impact of mental illness on the entire household.
Response
Dr Doherty agreed that this is a significant challenge and explained that her research is centred on improving whole-family support. She highlighted that current services often operate in silos, limiting opportunities for early intervention and joined-up care. The aim of her research is to identify practical ways of embedding the Think Family approach more effectively within adult mental health services.
Q2. How will the research address the inequalities experienced by ethnic minority families?
A discussion focused on the additional challenges faced by ethnic minority families, particularly where disability, poverty, language barriers and mental health intersect. Concerns were raised about institutional racism, unequal treatment and the fear some parents experience when engaging with services.
Response
Dr Doherty acknowledged that these intersecting inequalities can significantly affect families’ experiences. She recognised that services can often adopt a risk-focused rather than strengths-based approach and explained that her research seeks to identify earlier, more supportive interventions that better meet the needs of ethnic minority families.
Q3. How will carers participating in the research be protected from emotional harm?
The discussion explored the importance of safeguarding participants involved in research. It was suggested that sharing lived experiences can be emotionally challenging and that researchers should have appropriate support mechanisms in place before, during and after participation.
Response
Dr Doherty explained that safeguarding had been a key consideration throughout the development of the study. She described how support, supervision, training and ongoing review have been built into the project, alongside close collaboration with Experts by Experience from the earliest stages of the research.
Q4. Will participants receive ongoing emotional support after difficult discussions?
A further question explored whether structured debriefing and emotional support would be available for participants who may experience distress after discussing traumatic experiences.
Response
Dr Doherty confirmed that the study includes a comprehensive safeguarding framework, including debrief sessions and wellbeing support. She explained that the project had undergone rigorous NHS ethics approval and that participant welfare continues to be reviewed throughout the research process.
Q5. How is co-production embedded within the research?
The final discussion focused on ensuring that the research is genuinely co-produced with ethnic communities rather than being designed solely from a professional perspective. There was also support for developing safeguarding approaches jointly with carers.
Response
Dr Doherty explained that co-production is fundamental to the project. She has worked alongside Experts by Experience since the study was first developed and described the research as something being undertaken in partnership with people who have lived experience. She also welcomed suggestions for strengthening carer-led safeguarding approaches as the project progresses.
Dr Maeve (King’s College London)
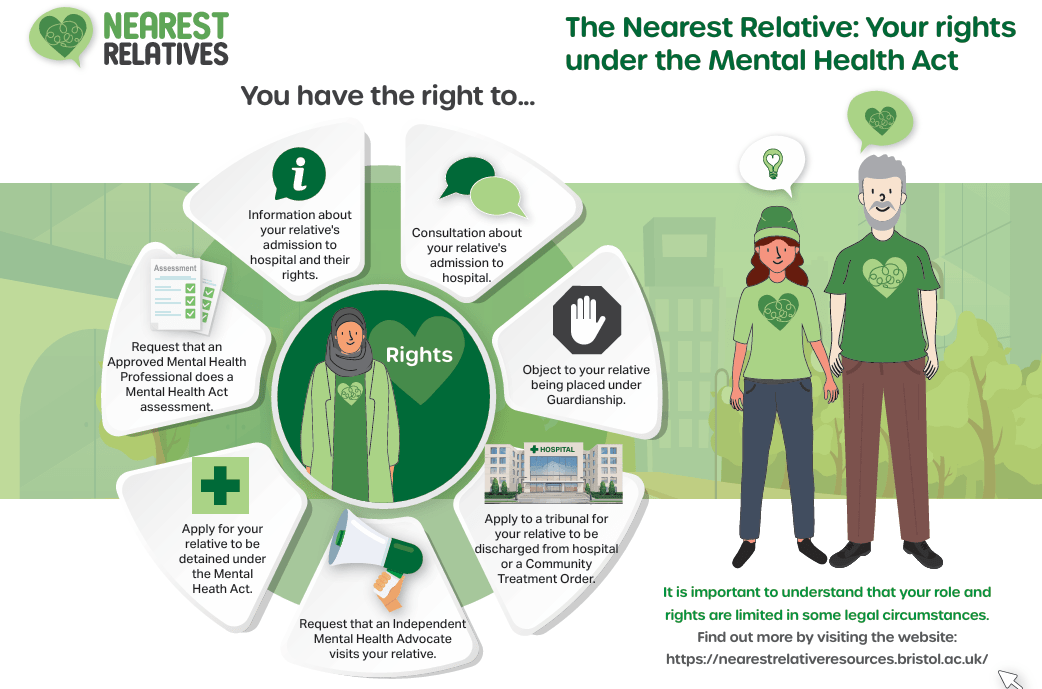
Research Study: The Nearest Relative under the Mental Health Act
Dr Maeve introduced a new King’s College London research project examining experiences of the Nearest Relative provisions within the Mental Health Act. She explained that the study aims to understand how the current legislation works in practice and gather views ahead of the proposed reforms to mental health law. The researchers are interested in hearing directly from people who have lived experience of the system, recognising that the Nearest Relative can play a crucial role in supporting someone during assessment, detention and treatment.
The study is seeking participants from a range of backgrounds, particularly unpaid carers who have supported someone detained or assessed under the Mental Health Act, as well as individuals who have themselves experienced detention or assessment. The research team is especially keen to hear from Black and other ethnic minority communities, along with younger people, to ensure that a wide range of perspectives help inform future policy and practice. Interviews are conducted online via Microsoft Teams at a convenient time for participants, last approximately one hour, and participants receive a £30 shopping voucher as a thank-you for contributing their experiences. Dr Maeve encouraged anyone interested to contact the research team or share the opportunity with others who may wish to participate.
Ruby Neish – University College London
Cancer Care and Black Women
Research Study: Supporting Carers of Women with Endometrial (Womb) Cancer
Ruby Neish, a Master’s researcher from University College London working in collaboration with the Centre for Early Detection, introduced a research project exploring the experiences of family members, friends and unpaid carers supporting women diagnosed with endometrial (womb) cancer. She explained that while much research focuses on the experiences of patients themselves, comparatively little is known about the challenges faced by those providing informal care throughout diagnosis, treatment and recovery. The study aims to build a more complete picture by understanding how carers experience the cancer pathway, the support they receive and the barriers they encounter. Ruby emphasised that carers often play a vital role in navigating appointments, providing emotional support, helping with treatment decisions and managing the practical realities of living with cancer, yet their experiences are frequently overlooked in research.
Following the presentation, forum members shared a wealth of lived experience highlighting why this research is particularly important for Black and minority ethnic communities. The discussion explored how delayed diagnosis, language barriers, cultural expectations, disability, poor communication and wider health inequalities can all contribute to poorer experiences for both patients and their families. Members also reflected on the importance of improving awareness of cancer symptoms within communities, encouraging uptake of screening programmes and ensuring services are culturally responsive. Several contributors stressed that carers often become advocates, interpreters and navigators of the healthcare system, particularly where individuals experience multiple forms of disadvantage. The discussion reinforced the importance of ensuring that future cancer services recognise and support carers as an essential part of the patient’s journey.
Questions and Discussion
Q1. Why is it particularly important to understand the experiences of Black and minority ethnic women living with cancer?
Forum members discussed how people from Black and minority ethnic communities can face additional barriers throughout the cancer pathway. These included language differences, lower awareness of symptoms, cultural beliefs about illness, disability, mental health needs and difficulties accessing appropriate support. It was suggested that these factors can contribute to delayed diagnosis and poorer outcomes if services fail to respond to people’s individual circumstances.
Response
Ruby welcomed these observations and explained that hearing directly from carers is essential to understanding these inequalities. She noted that while patients’ experiences are being explored separately, the research hopes to capture the perspectives of carers to identify barriers that may otherwise remain invisible. Together, these findings will help build a more complete understanding of how cancer services can better support families from diverse communities.
Q2. How can cancer services improve early diagnosis within ethnic communities?
The discussion highlighted the importance of encouraging earlier engagement with screening programmes and improving awareness of cancer symptoms within local communities. Examples were shared of women whose diagnoses were delayed after repeated visits to healthcare services, alongside reflections on the positive impact that culturally appropriate information and trusted community support can have in encouraging people to attend screening appointments. Participants emphasised that services need to communicate in ways that are accessible and sensitive to different cultural backgrounds.
Response
The discussion reinforced that improving awareness, reducing communication barriers and working more closely with communities could contribute to earlier diagnosis and improved outcomes. The research aims to identify where carers believe improvements can be made across the diagnostic and treatment journey, helping to inform future service development.
Q3. What role do unpaid carers play throughout the cancer journey?
A final discussion focused on the often unseen contribution of unpaid carers. Members described how carers frequently provide emotional reassurance, accompany relatives to appointments, help explain medical information, advocate for concerns to be taken seriously and support individuals throughout treatment and recovery. It was recognised that carers often become the link between patients, families and healthcare professionals, particularly where communication barriers or additional health conditions exist.
Response
Ruby explained that this is precisely why the study is focusing on carers’ perspectives. Understanding their experiences will provide valuable evidence about the practical and emotional challenges carers face and identify ways that cancer services can better recognise and support them alongside the person receiving treatment.
NHS England – Allied Health Professions Strategy
Steve Tolan (Deputy Chief Allied Health Professions Officer) & Barry O’Donovan (Senior Programme Manager)
Steve Tolan and Barry O’Donovan from NHS England joined the forum to begin an important conversation about developing a new national Allied Health Professions (AHP) Strategy. Rather than presenting a completed strategy for consultation, they explained that NHS England wanted to engage with carers, patients and communities before the strategy was written, ensuring that lived experience would help shape its priorities from the outset.
Steve introduced the Allied Health Professions as the third largest clinical workforce in the NHS, comprising fourteen professions including occupational therapists, physiotherapists, speech and language therapists, dietitians, radiographers and several others. He explained that these professionals work across virtually every part of health and care, from mental health and primary care to acute hospitals, rehabilitation and community services, making their contribution central to improving patient outcomes.
Barry explained that NHS England was seeking honest feedback on what Allied Health Professionals currently do well and, more importantly, where improvements were needed over the next five years. The discussion centred around several key questions, including how AHPs could help people stay healthier for longer, improve prevention, reduce health inequalities, remove barriers to accessing care, and work more effectively across different care settings. Forum members were also encouraged to complete a wider national survey, but NHS England emphasised that hearing directly from unpaid carers during the meeting would provide invaluable insight into the everyday realities experienced by families supporting loved ones with mental illness and other long-term conditions.
What followed was one of the richest discussions of the meeting, with carers sharing personal experiences of navigating health services and offering practical recommendations for change. Contributors acknowledged the important work undertaken by Allied Health Professionals but stressed that future success would depend upon moving beyond clinical interventions alone. Members called for greater emphasis on prevention rather than crisis management, stronger action to address racism and health inequalities, more personalised and culturally responsive care, improved communication with families and better recognition of unpaid carers as essential partners within the healthcare system. NHS England representatives listened carefully throughout the discussion, responding positively to the feedback and confirming that the experiences shared during the forum would help inform the development of the national strategy.
Feedback from Forum Members
There was a lot more feedback, but I have only included 4 feedback to the strategy
Feedback 1 – Prevention must become the priority, not simply responding to crisis
One of the strongest messages from the discussion was that health services often intervene too late. Contributors explained that many families recognise early warning signs long before services become involved, yet support is frequently unavailable until a situation has escalated into crisis. Members argued that Allied Health Professionals are well placed to identify emerging concerns earlier, particularly for people living with long-term mental health conditions, autism, learning disabilities and chronic physical illnesses. Earlier intervention, they suggested, would reduce avoidable hospital admissions while improving outcomes for both patients and carers.
NHS England acknowledged this feedback, explaining that one of the key ambitions of the new strategy is to support the wider NHS objective of shifting from reactive treatment towards prevention. Representatives welcomed examples from carers illustrating where earlier support could make the greatest difference.
Feedback 2 – Tackling racism and health inequalities requires more than training
Forum members spoke candidly about experiences of racism, discrimination and unequal treatment within health services. While acknowledging that cultural awareness training is becoming more common, contributors argued that training alone is insufficient unless accompanied by accountability and meaningful changes in practice. Some described inaccurate clinical records, assumptions based on ethnicity and situations where concerns raised by families were not properly reflected in care planning. There was a strong call for services to improve communication, record keeping and trauma-informed practice, ensuring that staff understand the impact of racism on health outcomes rather than viewing cultural competence as a one-off training exercise.
NHS England representatives recognised that tackling health inequalities and promoting anti-racist practice were already identified as “non-negotiable” priorities within the developing strategy. They explained that this was precisely why engagement with forums such as this was so valuable, helping ensure that policy reflects the real experiences of people using NHS services.
Feedback 3 – Unpaid carers must be recognised as equal partners in care
A recurring theme throughout the discussion was the role of unpaid carers within healthcare systems. Members explained that carers are often the people coordinating appointments, supporting communication, monitoring deterioration, providing emotional support and helping professionals understand an individual’s needs. Despite this, carers frequently remain unidentified by services or receive little information and support themselves. Contributors argued that Allied Health Professionals should routinely identify carers, involve them in care planning where appropriate and recognise them as equal partners whose knowledge can significantly improve patient outcomes.
NHS England welcomed these comments and recognised that carers play a fundamental role in delivering effective, preventative care. The examples shared demonstrated how stronger partnerships with carers could improve continuity of care while helping services better understand the needs of individuals and families.
Feedback 4 – Share and learn from examples of excellent practice
The discussion concluded with examples of positive experiences that illustrated what good care can look like. One contributor described receiving outstanding support from an Occupational Therapist who not only arranged practical adaptations within the home but also followed up afterwards to ensure everything was working well. Members suggested that NHS England should identify and promote examples of excellent practice across the Allied Health Professions so that high standards become the norm rather than the exception. Ideas included involving patients and carers more directly in evaluating services and using lived experience to help identify what compassionate, person-centred care looks like in practice.
West London Health Trust – PCREF Update
Linda Thomas – Co-producing an Independent PCREF Advisory Group
Linda Thomas, Co-production and Partnerships Development Manager at West London NHS Trust, opened the Trust’s presentation by describing how they have developed an independent PCREF Advisory Group designed to challenge, support and hold the Trust to account as a “critical friend.” Rather than creating a traditional advisory panel, West London NHS Trust commissioned three established community organisations GOS&D (Ealing), SHEWISE (Hounslow) and Managing Our Mental (Hammersmith & Fulham) to help design the model and understand how communities genuinely want to engage with mental health services. The approach seeks to increase diversity of voices, identify barriers preventing community involvement and rebuild trust between local communities and the Trust. Linda explained that members of the advisory group now sit alongside Trust leaders as equal partners on the Steering Group, while work is progressing to secure long-term funding to sustain the network and strengthen relationships with community organisations. The initiative demonstrates how co-production can move beyond consultation towards genuine shared decision-making between the NHS and the communities it serves.
Debbie Best – PCREF Carer Lead: Racial Trauma Workshops
Debbie Best, PCREF Carer Lead at West London NHS Trust, presented the development of the Trust’s Racial Trauma Workshops, which were co-designed alongside Natalie Mark (PCREF Lived Experience Lead), Dr Anne Aiyegbusi and Chief Nurse Gillian Kelly. Debbie explained that the workshops were created in response to the persistent racial inequalities experienced within mental health services, including disproportionate detention under the Mental Health Act, restrictive interventions, mistrust of services and the re-traumatisation experienced by many people from ethnic communities.
Rather than delivering traditional equality training, the workshops create reflective spaces where staff openly discuss difficult issues including trust, power, emotional labour, racialised assumptions and barriers to culturally safe care. Debbie emphasised that racial trauma affects not only patients but also carers and NHS staff, and that creating psychologically safe spaces for honest conversations is an essential step towards improving relationships, reducing inequalities and embedding the aims of the Patient and Carer Race Equality Framework (PCREF) across mental health services.
Christine – Triangle of Care, Carer Awareness Training and PCREF
Christine, speaking as a carer representative involved in co-production, highlighted how West London NHS Trust has successfully embedded carers within staff training through the Triangle of Care programme. She explained that the Trust achieved Stage 2 Triangle of Care accreditation in March 2026 and has developed Carer Awareness Training that is designed and delivered alongside carers themselves.
The training introduces staff to both the Triangle of Care and the Patient and Carer Race Equality Framework, helping colleagues understand the importance of recognising carers as equal partners while strengthening communication and collaboration with families. Christine also announced that West London NHS Trust has been selected as one of only thirteen national pilot sites testing the integration of Triangle of Care and PCREF guidance over the next twelve months. Ten clinical teams will take part in reviewing and implementing the updated guidance, ensuring that national best practice is informed by both professional expertise and lived experience.
Debbie Best – Ethnicity Data Capture Project
Debbie concluded the presentation by introducing West London NHS Trust’s Ethnicity Data Capture Project, funded through a small grant from the NHS Race and Health Observatory. She explained that the project aims to improve understanding of why ethnicity information is not always accurately recorded and why some communities remain reluctant to share this information. Working alongside community organisations including SHEWISE, Our Voices and Managing Our Mental, the Trust has co-produced a range of resources including information leaflets, awareness films, social media campaigns, frequently asked questions and staff training materials. The campaign, titled “Seen, Heard, Counted,” aims to reassure communities that ethnicity data is collected to improve healthcare, tackle inequalities and ensure services better reflect the needs of local populations. Debbie explained that the next phase of the project will focus on wider public awareness and rolling out staff training across the Trust to improve confidence, transparency and trust around ethnicity data collection.
Bren McInerney
Race Equality Observatory
Bren McInerney provided an update on behalf of the NHS Race and Health Observatory, explaining that although he works closely with the organisation through its Stakeholder Engagement Group, he was speaking from his role supporting engagement rather than as an NHS employee. He began by outlining the Observatory’s purpose, which is to identify, understand and help reduce ethnic inequalities across health and social care through research, evidence and partnership working.
Bren highlighted that the Observatory has now produced a growing body of evidence to support NHS organisations in tackling inequalities and emphasised that this work must ultimately lead to practical improvements in services rather than simply producing reports. He also noted that the Observatory’s current funding arrangement is due for renewal in 2027, making it increasingly important to demonstrate the value and impact of its work across the NHS. The presentation encouraged attendees to remain engaged with the Observatory’s programmes and continue sharing lived experience to strengthen the evidence base for future policy and service improvement.
Bren also highlighted several recent initiatives designed to strengthen collaboration between the NHS and local communities. These included the publication of the Trauma-Informed Care and Racialised Communities Report, which explores how trauma-informed approaches can better respond to the experiences of people affected by racism and discrimination. He also described the Observatory’s Small Grants Programme, which has supported community-led projects across England, and introduced a new Community Participation and Co-production Resource developed in partnership with the Race Equality Foundation. This resource aims to help NHS organisations and Integrated Care Boards build stronger relationships with communities, improve meaningful involvement in decision-making and ensure that local knowledge helps shape healthcare services. Bren concluded by encouraging carers, voluntary organisations and community leaders to make use of these resources, share them widely and continue influencing the national conversation on race equality within health services.
What does racial inequality in mental health really look like from the perspective of an unpaid carer?
In this powerful spoken-word poem, Matthew McKenzie explores the realities of racism, bias, exclusion, stigma, and unequal treatment experienced by many ethnic communities when accessing mental health services.
Through an A–R alphabet structure, this poem highlights why the Patient and Carer Race Equality Framework (PCREF) matters and why genuine cultural understanding, listening, and inclusion are essential to improving care.
This poem is part of my 100-poem PCREF collection, Unpaid, Unseen and Yet Unbroken, giving voice to the experiences of unpaid carers supporting relatives with mental illness while challenging racial inequalities across mental health services.
By Matthew McKenzie – Carers UK ambassador / Chair of National ethnic mental health carers forum
Are you a Black unpaid carer supporting a family member with a learning disability (sometimes referred to as an intellectual disability) who has experienced mental health difficulties?
Have you ever tried to access mental health support on their behalf? This could include contacting services such as Community Learning Disability Teams, CAMHS, Community Mental Health Teams, Talking Therapies or other mental health services.
If so, your experiences matter.
Lauren Heath, a second-year Trainee Clinical Psychologist at the University of Southampton, is conducting doctoral research exploring the experiences of Black carers who have accessed, or attempted to access, mental health support for a family member with a diagnosed learning disability.
We know that Black unpaid carers often face additional challenges when trying to navigate health and social care systems. Too often, their experiences are unheard or underrepresented in research. This study aims to better understand those experiences and help inform more culturally sensitive and inclusive services in the future.
You may be eligible to take part if you:
Identify as Black.
Have significant caring responsibilities for a family member with a diagnosed learning disability (or intellectual disability).
Have accessed, or attempted to access, mental health services on their behalf.
Taking part will involve:
A confidential interview lasting approximately 1.5 hours via Microsoft Teams.
Your responses will be anonymised once all interviews have been completed.
You will receive a voucher to thank you for your time and contribution.
Lauren previously worked within Community Learning Disability Teams across the UK and became interested in understanding why so few Black families appeared to be accessing these services. Her doctoral research hopes to amplify the voices of Black carers and contribute towards improving culturally sensitive support for families in the future.
If you think this research may apply to you, or someone you know, please consider taking part or sharing this opportunity within your networks.
To find out if you are eligible, you can complete the short questionnaire or contact Lauren directly at L.Heath@soton.ac.uk.
Your lived experience could help shape future services for Black families and carers.
By Matthew McKenzie – Triangle of Care – Community group chair
Putting Carers at the Centre of Care
The latest Triangle of Care Community Group brought together carers, professionals and partner organisations from across England to share learning, celebrate progress and identify where further improvements are needed. The meeting highlighted the growing influence of the Triangle of Care across mental health and acute services, whilst reinforcing that there is still much work to do to ensure carers are consistently recognised, valued and supported.
One of the most powerful aspects of the meeting was hearing directly from carers about their experiences. Whilst many spoke positively about the progress that has been made over recent years, there was a shared view that carer involvement remains inconsistent across services. Carers described feeling more included than ever before, with greater awareness of the Triangle of Care principles and more opportunities to participate in steering groups, service developments and community discussions. However, concerns remain around automatic carer identification, information sharing and ensuring that carers are genuinely recognised as partners in care.
Several carers reflected on the importance of having their voices heard early in a patient’s care journey. Examples were shared of services introducing carer contribution templates that ensure family members are involved within 72 hours of admission, whilst others highlighted improvements to confidentiality processes that allow patients to determine what information can be shared with carers at different stages of their recovery. These practical changes demonstrate how relatively small adjustments can have a significant impact on relationships between carers, patients and professionals.
Progress Across the Triangle of Care Programme
Mary Patel, Triangle of Care Programme Lead at Carers Trust, provided an update on developments across the national programme. The Triangle of Care continues to grow, with a number of organisations progressing through the STAR accreditation process and demonstrating their commitment to embedding carer-inclusive practice across services.
Importantly, members were reminded that the STAR awards are not designed to rank organisations, but instead reflect the breadth of implementation across different service areas. STAR I focuses primarily on inpatient and crisis services, STAR II expands into community services, whilst STAR III recognises organisations delivering integrated services across multiple clinical areas.
Several trusts have recently achieved STAR awards, whilst others are progressing through the assessment process over the coming months. The programme’s peer review approach continues to ensure that carers remain central to the assessment process, with carers actively involved in reviewing evidence, identifying good practice and making recommendations for future development.
The Triangle of Care Member Hub continues to provide valuable opportunities for peer learning, resource sharing and collaborative working. Upcoming webinars will include sessions exploring Open Dialogue approaches developed by Devon Partnership NHS Trust, providing members with further opportunities to learn about therapeutic models that place families and carers at the heart of care planning.
Advancing Equality Through the Patient and Carer Race Equality Framework
A significant development announced during the meeting was the launch of Phase Two of the Triangle of Care and Patient and Carer Race Equality Framework (PCREF) project.
PCREF represents the first mandatory anti-racism framework within mental health services in England. Recognising that carers from racially marginalised communities often experience poorer outcomes and face additional barriers when accessing support, the Triangle of Care programme has been working collaboratively with carers and mental health providers to strengthen the way services assess and respond to carers’ needs.
The revised self-assessment framework encourages services to move beyond assumptions and adopt a more professionally curious approach to understanding carers’ individual experiences. Rather than viewing carers as a homogenous group, the framework recognises that caring experiences are shaped by culture, identity, language, personal circumstances and wider health inequalities.
Pilot sites from across England are now testing the revised guidance, with learning being shared nationally throughout the project. Importantly, organisations do not need to be participating in the pilot to begin implementing the principles and learning that emerge from this work.
Alongside PCREF, Carers Trust continues to contribute to national policy developments, including the Modern Service Framework for Severe Mental Illness and the forthcoming Mental Health Strategy for England. Throughout these discussions, there has been a consistent message that carers must be recognised as partners in care and have access to appropriate support in their own right.
Confidentiality, Information Sharing and Carer Inclusion
Confidentiality remained one of the most prominent themes throughout the meeting. Whilst participants acknowledged the importance of protecting patients’ rights and preferences, carers highlighted that confidentiality can sometimes become a barrier to meaningful engagement.
Several contributors reflected that confidentiality should never prevent professionals from listening to carers’ concerns or receiving valuable information that may support a patient’s care. Others spoke about the importance of revisiting conversations around consent over time, recognising that patients’ preferences may change as their circumstances and wellbeing improve.
Practical examples of good practice included breaking confidentiality discussions down into specific areas, allowing patients to decide what information can be shared about medication, activities, wellbeing and treatment plans, rather than relying on simple ‘yes or no’ decisions. There was also discussion around the importance of staff training to improve confidence when navigating complex conversations around confidentiality and information sharing.
Participants agreed that carers should never be expected to provide significant levels of support without receiving the information necessary to do so safely and effectively. Achieving the right balance between confidentiality and partnership working remains an important priority for the Triangle of Care community.
Triangle of Care Principles Within Acute Services
The meeting concluded with an inspiring presentation from Wendy Doyle, Head of Patient Experience at St George’s University Hospitals NHS Foundation Trust and Epsom and St Helier Hospitals, exploring how Triangle of Care principles can be successfully implemented within acute hospital settings.
Whilst the Triangle of Care originated within mental health services, Wendy demonstrated that its principles are equally applicable across acute care environments. Her organisation supports approximately 19,000 members of staff across multiple hospital sites and has developed a comprehensive approach to identifying, recording and supporting unpaid carers.
Staff are encouraged to identify carers at the earliest possible opportunity, with this information recorded within patient records to ensure continuity throughout the patient’s hospital journey. Comprehensive carer awareness training is delivered through virtual sessions, ward-based education and e-learning resources, helping staff understand both the practical and emotional importance of recognising carers.
Importantly, identifying carers is only the beginning of the process. Every carer recorded within the hospital system receives a follow-up wellbeing check from the Patient Experience Team to discuss their own support needs, identify any challenges and facilitate referrals to local carers’ organisations where appropriate.
Partnership working sits at the heart of this approach, with close collaboration between acute services and local carers’ centres ensuring carers can access a broad range of practical and emotional support. Adult and Young Carers’ Charters have also been co-produced with carers themselves, helping to shape organisational commitments around kindness, inclusion and meaningful engagement.
Perhaps most importantly, Wendy highlighted that supporting carers improves outcomes for everyone. Better communication strengthens discharge planning, reduces avoidable hospital admissions and readmissions, improves patient safety and helps prevent carer burnout. Acute hospital stays can provide valuable opportunities to identify carers who may previously have remained invisible and connect them with longer-term support.
Looking Ahead
The discussions throughout the meeting demonstrated both the progress that has been made and the challenges that remain. There is increasing recognition that carers are essential partners in delivering high-quality care across both mental health and acute services. However, meaningful involvement cannot rely upon individual goodwill alone; it requires consistent systems, robust policies and a genuine commitment to partnership working.
Looking ahead, the Triangle of Care programme will continue to expand opportunities for peer learning, influence national policy developments and support organisations to embed carer-inclusive practices across services. The ongoing work around PCREF and wider mental health policy developments provide important opportunities to ensure that carers’ voices remain central to future service transformation.
Above all, the meeting reinforced a simple but powerful message: carers must not be viewed as an afterthought or an optional addition to care planning. They are experts through experience, invaluable partners in care and individuals with support needs of their own. When carers are identified early, listened to meaningfully and supported appropriately, outcomes improve not only for carers themselves, but for patients, families and services alike.
The Triangle of Care Community Group continues to provide an important space where carers and professionals can learn from one another, challenge existing practices and work collectively towards more compassionate, inclusive and effective care.