As International Stress Awareness Week 2026 draws to a close, I want to highlight the pressures carried by unpaid carers and why their wellbeing must remain part of the conversation throughout the year.
Supporting a relative or friend can mean balancing appointments, employment, financial worries and disrupted sleep. Even during a quiet moment, a carer’s mind may still be on duty, thinking about what might happen next.
In my latest Caring Mind video, I explore these pressures and share some practical ways carers can find support.
Recognising the person behind the caring role
Carers need opportunities to speak honestly about stress without feeling guilty or judged. For some ethnic minority carers, racism, language barriers and having their concerns dismissed can add further pressure.
Taking a short break, enjoying poetry or music, or talking with someone supportive may help. Asking for specific practical assistance such as shopping or help with a caring task can also make space to rest.
However, reducing carer stress requires more than individual coping strategies. Reliable services, understanding employers, accessible information and meaningful involvement in care decisions all matter.
Please watch and share the video, and take a moment to ask an unpaid carer how they are coping. Listen to the answer, and consider what help you could offer.
The awareness week may be ending, but our responsibility to support unpaid carers continues.
By Matthew McKenzie – Chair, National Ethnic Mental Health Carers Forum
Welcome to my October update from the National Ethnic Mental Health Carers Forum. I am Matthew McKenzie, and I chair this forum to give unpaid mental health carers from ethnic minority communities a space to share experiences, question services and connect with people working to improve care.
Our meeting on Friday 30 October brought together presentations and discussion about racial inequalities, the wellbeing of unpaid carers, and the difficulties families face when trying to secure appropriate mental health support.
We heard from Tracy Bignall from the Race Equality Foundation and carer campaigner Agi, who presented findings from a substantial piece of work with carers in East Sussex. Their presentations approached change from different directions: challenging structural racism across institutions, and gathering carers’ experiences to press for improvements within local services.
Throughout the meeting, a shared concern emerged. Carers are often expected to hold care together, yet their knowledge, health and support needs can receive too little attention.
Tracy Bignall – Race Equality, Unpaid Caring and Mental Wellbeing
Tracy Bignall, Director of Policy Engagement at the Race Equality Foundation, introduced the organisation’s work to improve experiences and outcomes for Black, Asian and minority ethnic communities.
She explained that the Foundation works through research, evidence, practical interventions and partnerships to challenge discrimination and disadvantage. Its work extends across health inequalities, family support and other areas affecting people’s lives.
For this forum, Tracy focused on the relationship between unpaid caring, ethnicity and mental wellbeing. She highlighted the pressures caring can place on employment, household finances, physical health and emotional wellbeing. These pressures can become particularly demanding for people balancing caring with paid work, raising children or supporting ageing parents.
Recognising yourself as a carer
An important part of Tracy’s presentation concerned who identifies with the word “carer”.
For some families, supporting a relative is understood primarily as a family responsibility. People may describe themselves as a parent, partner, sibling or adult child without recognising that they are also providing unpaid care.
Language and cultural expectations can influence this recognition. The term “carer” may not translate easily into someone’s understanding of their role, and seeking help may feel unfamiliar or uncomfortable.
This matters because people who do not identify as carers may miss information, assessments, peer support or other assistance. Services need to explain what caring means in ways that connect with people’s everyday lives.
Racism, financial pressure and trust in services
Tracy explained that carers’ wellbeing must be understood within the wider circumstances of their lives.
Financial pressure can reduce opportunities to meet friends, enjoy hobbies or take part in activities that support mental wellbeing. For someone already carrying substantial caring responsibilities, losing those opportunities can deepen isolation.
She also discussed the cumulative impact of racism and discrimination across education, employment, healthcare and later life. These experiences can affect mental wellbeing and influence whether people feel safe approaching services.
Where communities have experienced discriminatory treatment, encouraging people to seek support requires more than providing information. Services must address the experiences that have damaged trust.
Moving towards structural change
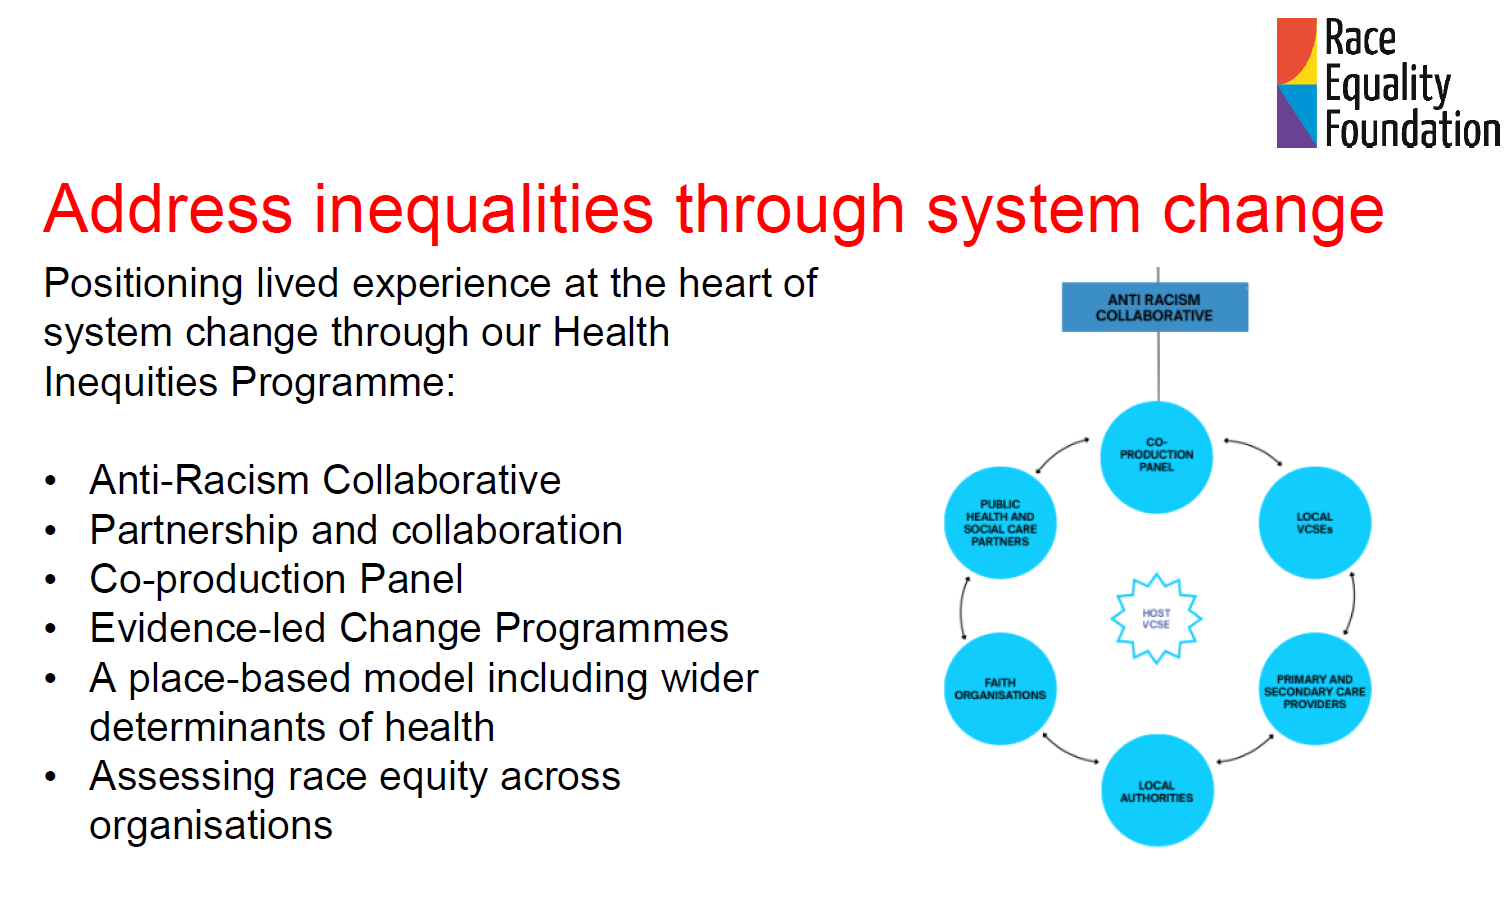
Tracy described the Foundation’s work through the London Anti-Racism Collaboration for Health programme, which I had previously contributed to.
The programme brought together partners from the NHS, public health, local government, social care, voluntary organisations and communities. Its purpose was to help institutions take an active anti-racist approach to health inequalities, including examining policies, commissioning and workforce practices.
She also discussed work developing recommendations on structural racism and the wider determinants of health. Housing, the environment and other conditions shape people’s wellbeing, so improving health requires action beyond healthcare appointments.
Tracy then introduced a five-year programme developing anti-racist collaboratives in selected areas. A central feature is the involvement of people with lived experience in identifying priorities and shaping decisions.
The programme creates opportunities for communities and organisations to use evidence, test approaches and share learning. Support for unpaid carers could become a focus where communities identify it as a local priority.
Discussion Following Tracy’s Presentation – Accessibility, Culture and Meaningful Co-production
The discussion brought Tracy’s presentation into contact with the practical concerns carers encounter.
Older carers and isolation
Members raised the needs of older carers who are managing their own health conditions or mobility difficulties while supporting someone else.
There was particular concern about isolation during winter and about support that assumes everyone can travel or participate online.
Tracy clarified that the Foundation primarily works through research, policy, partnerships and support for organisations, rather than providing a general frontline carers service. She described previous work supporting organisations assisting older people and families affected by dementia, including efforts to help smaller community organisations access funding.
The exchange highlighted the importance of sustaining trusted local organisations that already have relationships with carers.
Accessible information requires more than translation
Members questioned whether written translations are enough to make information accessible.
Speaking a language does not necessarily mean someone can comfortably read it. Equally, speaking conversational English does not mean someone can understand a complex letter about care.
The discussion identified a need for different formats, including:
Plain language and Easy Read information.
Pictures and visual explanations.
Spoken information and short videos.
British Sign Language and appropriate interpreting support.
Clear explanations of available services and how to access them.
Tracy described the Foundation’s use of different formats and work developing information about access to interpreting support within the NHS.
A recurring concern was that people cannot use support they have never been told exists. Accessibility therefore includes how services explain and promote what is available.
Cultural needs and disabled parent carers
Members described situations in which carers felt their cultural needs were poorly understood or dismissed.
Concerns included preferences around intimate personal care, assumptions about family responsibilities, and the experiences of disabled people who also care for someone else.
The discussion challenged the idea that receiving support for your own disability prevents you from being a carer. People can occupy both roles, and services need to understand the whole family situation.
Tracy acknowledged the difficulties and emphasised the importance of personalised care, informed challenge and working through trusted community organisations.
Co-production must influence decisions
Another important question concerned how to make co-production work in practice.
Tracy described an anti-racist co-production resource being developed with partners. She also highlighted a familiar tension: communities may explain clearly how information should be presented, only for institutions to favour their established wording and processes.
The discussion reinforced that asking people to contribute is only part of co-production. Organisations must be willing to give those contributions weight and change their approach.
For carers, this means being able to see how their involvement has affected decisions, communication or care.
Agi – Turning East Sussex Carers’ Experiences into Evidence for Change
Agi presented findings from a report developed through the experiences of unpaid carers supporting adults with serious mental illness in East Sussex.
She spoke about her own long experience of caring and how attending a carers group helped her recognise that role. Through those meetings, she repeatedly heard similar concerns about communication, crisis support, exclusion and difficulties navigating services.
The report grew from a desire to bring those experiences together and present them to the local mental health trust as evidence requiring a response.
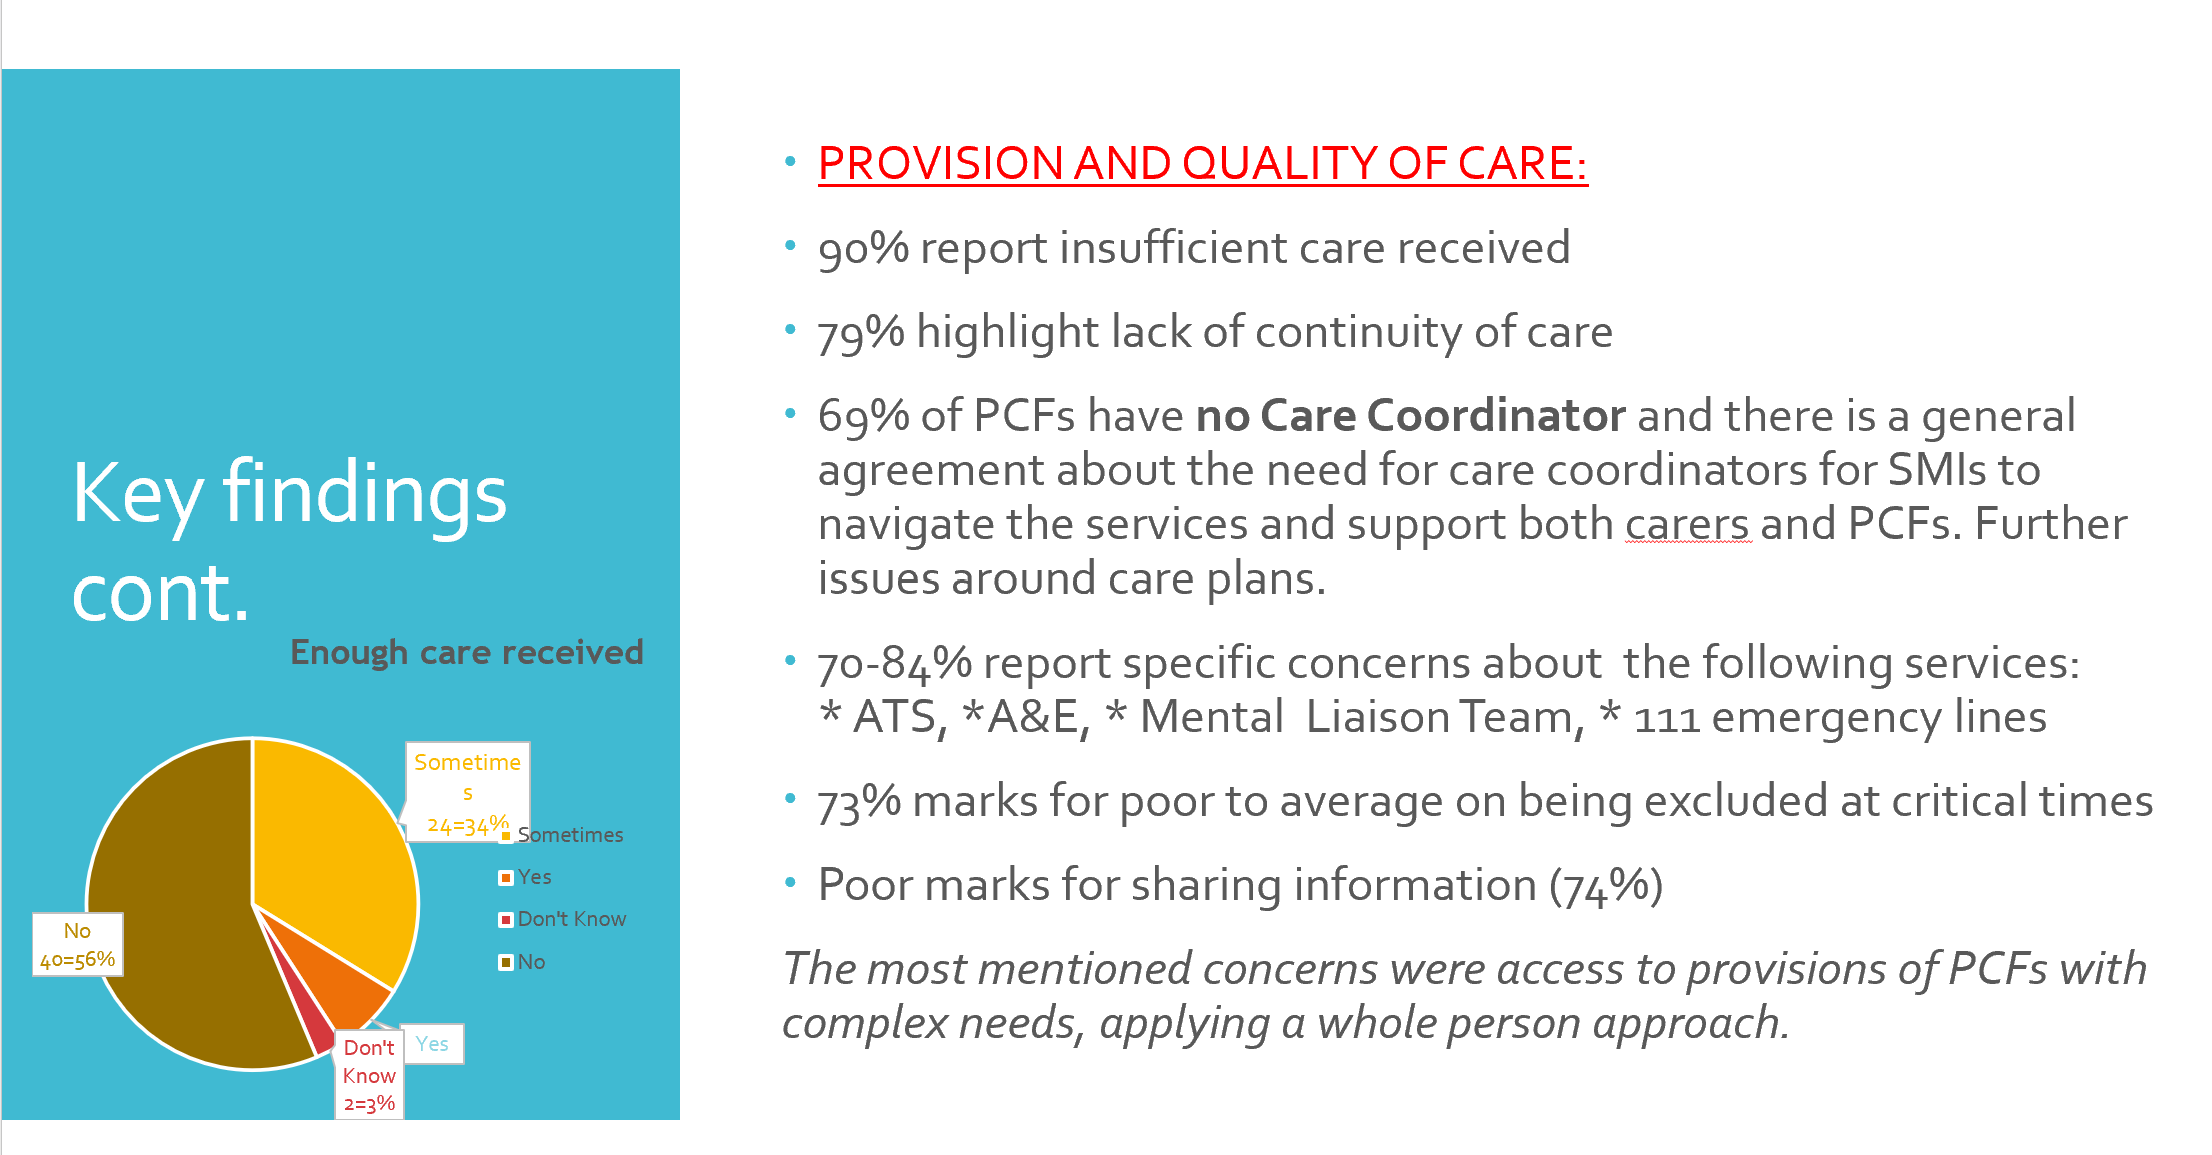
The work used a questionnaire containing 15 rated questions and two open-ended questions exploring carers’ concerns and suggestions. Agi described contributions from 71 carers supporting around 80 people.
These were findings from a particular group of respondents. However, many of the issues strongly resonated with those attending our national forum.
Long-term caring and complex responsibilities
Agi described a respondent group containing many women, older carers and people who had been caring for more than 15 years. Many supported adult children.
The report also highlighted complex needs, multiple diagnoses and the additional demands placed on people caring for more than one person.
These findings raised questions about how services assess the scale of someone’s caring responsibilities. Supporting one relative can already involve substantial work; caring for several people can leave very little space for the carer’s own health and wellbeing.
Responsibility without sufficient involvement
A central finding was that carers often felt they carried excessive responsibility while receiving limited professional support.
Respondents described having to advocate repeatedly to secure care, while not always feeling listened to or respected.
This is a serious tension within mental health care. Families may be relied upon to notice deterioration, manage difficulties at home and support recovery, yet struggle to be included when decisions are made.
Agi’s recommendations called for stronger partnership with carers, including practical implementation of the Triangle of Care.
Communication and information sharing
Communication emerged as a major area of concern.
Agi reported that 86% of respondents said they were informed about decisions, meetings or services only sometimes or not at all.
Carers wanted clearer, more consistent communication between teams and with families. They also wanted timely responses, accessible information and less jargon.
Poor communication places additional work on carers. They may have to chase updates, repeat information and work out which service is responsible, while also supporting someone who is unwell.
Consent and confidentiality
The report highlighted the stress created when consent and confidentiality are applied rigidly, particularly during crises or inpatient care.
Agi called for better staff training and clearer communication about what can be shared and how carers can contribute.
An important point in her presentation was that restrictions on disclosing information should not prevent staff from listening to information carers need to provide.
Families may hold essential knowledge about changes in behaviour, previous treatment, medication difficulties or emerging risks. A meaningful partnership needs a reliable route for that information to reach the care team.
Continuity and the importance of care coordination
Agi reported that 90% of respondents felt the person they supported had received insufficient care, while 69% said the person had no care coordinator.
She described continuity as one of the report’s strongest themes. Carers whose relatives had a care coordinator reported better experiences, and the report called for stronger coordination across services.
The value of a coordinator was explained in practical terms: someone who knows the person, understands the family context, follows up concerns and helps connect different parts of the system.
For people who find it difficult to engage with unfamiliar professionals, a trusted and consistent relationship can be particularly important.
Crisis support when families need it most
Agi described concerns about reaching crisis services, lengthy waits and the suitability of busy emergency departments for people experiencing severe mental distress.
Carers wanted responsive support outside normal working hours, clearer routes to help and more home-based interventions where appropriate.
The report also raised concerns about suicide prevention, aftercare and whether plans developed within services were reaching families in a useful form.
The question running through this section was straightforward: when a family reaches crisis point, can they obtain timely help that responds to the situation they are facing?
A broader approach to care and recovery
The report called for more individualised, therapeutic and holistic care.
Carers wanted greater attention to family work, psychological support, housing, financial advice, meaningful activities and complex or neurodiverse needs.
Agi also explained that the existence of a community activity or service does not guarantee that someone can use it. A person may need sustained support and a trusting relationship before they feel able to participate.
Recommendations therefore need to address the steps between offering a service and enabling someone to benefit from it.
Taking the findings to decision-makers
Agi described presenting the report to senior leaders and developing further conversations with the trust, including its Patient Advice and Liaison Service.
She acknowledged that learning how to work with institutional structures and constraints takes time. Her aim remained to secure practical improvements that carers and the people they support could experience.
The report offered a way to move repeated concerns from individual conversations into a collective account that services could examine and respond to.
Discussion Following Agi’s Presentation – Racial Trauma, Diagnosis and Advocacy
Members recognised many of the report’s findings and explored where further attention was needed.
Racial trauma must be explicitly recognised
The discussion raised the importance of trauma-informed care that recognises racism and racial trauma.
Members described how racial inequality, Islamophobia, disability-related barriers and gender could interact with the difficulties already identified in the report.
Agi acknowledged that the largely White respondent group meant racial inequalities had not emerged as a major distinct theme. She explained that trauma-informed support featured in the report, while recognising the need to give racial experiences greater attention.
For our forum, this was an important distinction. A general account of poor care may capture some shared experiences while still missing the specific barriers faced by ethnic minority families.
Late diagnosis and lack of diagnosis
Members also raised concerns about late diagnosis and situations where people remain without a diagnosis despite substantial difficulties.
Families can spend long periods providing support while struggling to secure assessment, recognition or an appropriate response.
The discussion highlighted the uncertainty and exhaustion this creates. Caring responsibilities continue even when a clear pathway into services has not been established.
Agi recognised this as an issue requiring further attention, although it had not been fully captured by the questionnaire.
The role of advocacy
An advocacy contribution to the discussion explored how independent support can help people understand options, raise concerns and challenge decisions.
Members considered advocacy in relation to hospital care, community services, assessments and complaints. There was also interest in further information or training so carers could better understand different forms of advocacy.
The discussion showed that awareness alone is insufficient. People need to know which service is relevant, how to contact it and what support it can provide in their circumstances.
There was particular concern that carers’ perspectives should remain visible in conversations about advocacy and mental health reform.
Planning ahead and recording preferences
Advance choice statements and planning during periods when someone feels able to participate were also discussed.
Examples included recording preferences about family involvement, treatment concerns and cultural needs. Hair care, food and personal care were raised as practical aspects of dignity that can easily be overlooked.
However, members also explained why planning ahead can be difficult. Someone experiencing persistent or recurring distress may have limited opportunities to engage with paperwork or unfamiliar professionals.
This brought the conversation back to continuity. Families may need help from a trusted professional to make planning possible and revisit it over time.
Trust connects people to support
One of the strongest points in the discussion was that numerous available services can still feel inaccessible.
A person experiencing psychosis or severe distress may find it difficult to trust new professionals or engage with another referral. Carers may then be expected to bridge every gap.
Members described the need for consistent relationships that help connect the person, family and different services.
Advocacy, care coordination and community support can each contribute. Their usefulness depends partly on whether the person can access them and whether someone helps make those connections.
Matthew McKenzie – Reflections on Partnership, Consent and Carers’ Relationships
As chair, I was struck by how closely the two presentations connected.
Tracy’s presentation asked us to consider the structures that produce and sustain racial inequalities. Agi’s presentation showed how carers can gather evidence of everyday service difficulties and use it to seek change.
Both made clear that listening needs to lead somewhere.
During the closing discussion, I reflected on the pressure that consent difficulties can place on the relationship between a carer and the person they support.
A carer may be trying to obtain urgent help while also preserving a relationship built over many years. Repeatedly having to intervene can create strain, particularly if the person experiences the carer as part of an unwanted service response.
Services need to recognise that relationship as an essential part of the situation. Carers should receive clear information about available support, opportunities for planning and how concerns can be communicated. These conversations also need revisiting as circumstances change.
There was considerable interest in returning to consent, confidentiality, advocacy and advance planning at a future forum.
The depth of discussion meant that we ran beyond our planned time and could not hear all the scheduled contributions. I am grateful to our speakers and everyone who contributed their experience, questions and ideas.
Continuing the Work
October’s forum reinforced the need for racial equality work and carer involvement to remain closely connected.
Carers need accessible information, culturally responsive support, reliable communication and recognition of their own wellbeing. People receiving care need relationships and services that recognise their individual circumstances, preferences and aspirations.
The meeting also demonstrated the value of bringing national policy work and local carer evidence into the same space. Each can strengthen the other, helping us ask more precise questions about what needs to change and how progress will be recognised.
Thank you to Tracy Bignall and Agi for sharing their work, and to everyone who helped make this such a thoughtful discussion.
I will continue using the National Ethnic Mental Health Carers Forum to bring these experiences together, encourage challenge and keep attention on the changes that matter to carers and their families.
As I continue developing my poetry collection Unpaid, Unseen and Yet Unbroken: Poetry about Ethnic Mental Health Carers, I wanted to share another poem from the collection called Language as Comfort.
This is Poem 30 and explores something that can easily be overlooked when we talk about involvement in mental health services: the comfort and belonging that can come from being able to communicate in your own language.
Watch the poem below.
For many ethnic minority carers, language is about much more than translating individual words. Our mother tongue can be connected to family, culture, identity, memory and a feeling of safety.
When language becomes part of carer inclusion
Language barriers can affect how confidently carers participate in assessments, consultations and discussions about the person they support.
This is why one part of the poem asks services to record a carer’s language needs:
A carer should not have to start again at every appointment, repeatedly explaining how they need information to be communicated.
This connects strongly with the Patient and Carer Race Equality Framework (PCREF). If we want meaningful involvement from diverse communities, we need to think about whether our usual ways of communicating actually enable people to participate.
The poem ends with the idea of language helping someone to “break free from this cage”.
For me, that is the central message of Language as Comfort. Being understood can create confidence. Being able to communicate can create involvement. And recognising someone’s language can help create a sense of belonging.
Language should not be another barrier between carers and mental health services.
It can instead become part of the bridge.
Poem 30 from the developing collection Unpaid, Unseen and Yet Unbroken: Poetry about Ethnic Mental Health Carers.
As I continue developing my poetry collection Unpaid, Unseen and Yet Unbroken: Poetry about Ethnic Mental Health Carers, I wanted to share another poem from the collection called Fear Has Roots.
The poem explores something I feel mental health services need to understand more deeply: mistrust does not always begin with the person standing in front of you.
Sometimes it has a history.
A carer may have experienced years of being dismissed, misunderstood or having their concerns minimised. They may have watched other carers from their community struggle to be heard. Experiences of discrimination can also travel through families and communities, influencing how safe people feel when approaching services.
By Matthew McKenzie – Chair of ethnic MH Carer forum / Chair of Cancer Carergiver group
I was recently sent information about an important cancer care project being led by Learning Disability England in partnership with the Race Equality Foundation which is funded by Macmillan Cancer Support.
The project aims to improve cancer care for people with learning disabilities from Black, Asian and minoritised ethnic communities. A working group is being established involving self-advocates, family members and friends who have experience of cancer.
Healthwatch Lambeth is inviting patients and unpaid carers to share their experiences of leaving hospital.
The survey is part of a nationwide Healthwatch England project examining hospital discharge. Healthwatch Lambeth is particularly seeking responses from people living in Lambeth who have experienced a difficult hospital discharge within the past 12 months.
This may include situations where:
Discharge was delayed.
The patient was sent home before they felt ready.
Information about the discharge was unclear or incomplete.
Essential equipment or support was not available.
Follow-up care had not been properly arranged.
An unpaid carer was not sufficiently involved, informed or prepared.
The survey can be completed by patients themselves or by an unpaid carer describing the experience of someone they care for.
Healthwatch Lambeth is especially interested in hearing from people whose experiences may not always be represented in health and care feedback, including men and people from ethnic minority communities.
Hospital discharge can place significant responsibility on families and unpaid carers. When carers are not recognised, involved or given the right information, they may suddenly find themselves managing medication, personal care, appointments and recovery without adequate preparation.
Sharing these experiences can help identify what needs to improve and highlight the importance of involving carers as genuine partners throughout discharge planning.
Please share this survey with Lambeth residents, patients and unpaid carers who may have had a difficult hospital discharge experience during the past year.
Black unpaid carers can face significant barriers when trying to access mental health support for themselves or the person they care for.
These difficulties may include long waiting times, financial pressure, cultural stigma, fear of statutory services and a shortage of professionals who understand the effects of racism, racial trauma and culturally specific caring experiences.
In my new video, I examine how misdiagnosis, over-policing and expectations that Black families should simply remain “strong” can create mistrust and discourage carers from asking for help.
Drawing on my perspective as a Black lived-experience carer, I also consider what mental health services can do differently. Genuine improvement requires culturally responsive support, greater representation, safe spaces for carers, accessible community-led services and meaningful partnership with Black carers and families.
PCREF provides an important opportunity to challenge racial inequalities, but its success will depend on whether services listen to lived experience and turn commitments into visible action.
By Matthew McKenzie – Ethnic Mental Health Carer and Poet
invisible challenge for ethnic minority mental health carers. “Poem 15: The friends I have lost,” a powerful spoken-word piece from Matthew McKenzie’s poetry book that is in development Unpaid, Unseen and Yet Unbroken, sheds a crucial light on this hidden struggle.
It captures the profound loneliness of an unpaid carer who watches friendships fade away as community members close their ears and elders demand privacy over open support. By highlighting the intersection of familial duty, mental illness, and societal rejection, this moving presentation exposes the heavy emotional toll born by those who care for loved ones behind closed doors.
This poem serves as a stark reminder of why initiatives like the Patient Carer Race Equality Framework (PCREF) are so urgently needed in healthcare and community support networks today.
Watch the full poetry video to immerse yourself in this essential conversation, and help us raise awareness for the vital support and recognition that ethnic minority mental health carers truly deserve.
By dismantling the barriers of stigma and addressing the specific inequalities faced by ethnic minority families, PCREF aims to ensure that no carer is left to navigate this challenging journey in absolute isolation.
By Matthew McKenzie – Carer & Chair of the National Ethnic MH carer Forum
The June 2026 National Ethnic Mental Health Carer Forum brought together carers, NHS Trusts, researchers, voluntary organisations and mental health professionals from across England to discuss one shared ambition improving mental health services through genuine co-production with ethnic minority carers.
Matthew reminded delegates that carers develop expertise through lived experience. Supporting a family member with severe mental illness means navigating NHS services, social care, benefits systems and advocacy. These experiences provide knowledge that cannot be learned through textbooks alone.
Opening Presentation
Matthew McKenzie
The Importance of Co-production
Forum Chair Matthew McKenzie opened the meeting by welcoming carers and professionals from across England and reflecting on more than a decade of leading the National Ethnic Mental Health Carer Forum.
This week as of this blog post, the London Assembly published a major new report on unpaid carers: “London’s unpaid carers: Caring for the carers.”
I had the opportunity to contribute to this work as a carer and advocate, alongside others who shared their lived experience. Seeing those voices reflected in the final report is both encouraging and a reminder of how much still needs to change for unpaid carers in London.
One of the strongest messages in the report is that many unpaid carers are still not identified.
Too often, people caring for a partner, parent, or child don’t even realise they are classed as a “carer” which means they miss out on financial support, services, and basic recognition.
From my own experience, and what was shared at the Assembly, this is especially true for:
Mental health carers
Carers from ethnic minority backgrounds
Indentification of unpaid carers
If you’re not identified, I feel you don’t exist in the system.
Financial pressure is a major issue
The report possibly confirms what many carers already know:
Nearly 1 in 3 carers in London are living in poverty
Carer’s Allowance is not enough to live on
Many carers have to reduce work or leave employment entirely
There are positive recommendations here like reviewing Carer’s Allowance and reducing travel costs, but these need to turn into real change, not just policy discussions.
Support isn’t working as it should
Another issue raised in the report and something I spoke about is that support often feels like a “tick-box exercise”.
Carers go through assessments, but:
Support is limited
Funding is inconsistent
Real help (like respite care) is hard to access, especially for mental health carers, I mean what does respite actually mean for mental health unpaid carers?
Identification alone isn’t enough. I think It has to lead to meaningful, practical support.
So what needs to happen next?
The report makes some important recommendations:
Better identification of carers across London
More funding for local carer services
Changes to Carer’s Allowance
Improved workplace support
and a lot more, but you would have to go through the report.
But the key question now is: will this actually be implemented?
Carers don’t need more recognition alone we need action.
Final thoughts
Unpaid carers are holding up the health and social care system every single day.
This report is a very important step forward. But it should be the beginning of change not the end of the conversation.
If you are a carer, or know someone who is, I’d encourage you to read the report and share your experiences. The more visible carers are, the harder it is for the system to ignore us.